How the Anion Gap Helps in Salicylate Poisoning
The anion gap is a valuable clue in the assessment of salicylate poisoning, but it should not be treated as a single diagnosis. In toxicology, the gap helps identify hidden acids in the blood and guides the broader acid-base balance assessment. Because aspirin exposure can produce more than one disturbance at the same time, the anion gap is often part of a larger laboratory interpretation rather than a single decisive number.
Classic aspirin toxicity often creates a mixed acid-base disorder. Initially, salicylates stimulate the respiratory center, leading to respiratory alkalosis through compensatory hyperventilation. As the poisoning advances, organic acids and impaired metabolism contribute to metabolic acidosis. The result is a pattern that can appear unclear if you focus only on one value. The anion gap becomes a diagnostic clue that helps connect the serum chemistry findings to the underlying toxicology evaluation.
Salicylates interfere with cellular metabolism and can disrupt oxidative phosphorylation, which promotes MUDPILES mnemonic explanation the accumulation of organic acids. These metabolic derangements lower buffering capacity and may increase the anion gap. At the same time, patients may present with tachypnea, nausea, vomiting, altered mental status, or other signs of systemic toxicity. In this setting, the anion gap supports clinical correlation rather than replacing it.
A normal or only mildly elevated anion gap does not exclude salicylate poisoning, especially when the acid-base pattern is evolving.
How to Apply an Anion Gap Calculator
An anion gap calculator is a practical tool for rapid laboratory interpretation during emergency assessment and poisoning workup. The usual calculation usually uses serum sodium, serum chloride, and serum bicarbonate. In its standard form, the formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Using the calculator begins with correct serum chemistry values. Initially, enter the sodium concentration. Afterward, add the chloride and bicarbonate concentrations. Deduct that sum from sodium to obtain the gap. This basic anion gap calculation can rapidly identify whether there is an abnormal accumulation of unmeasured anions.
In suspected salicylate poisoning, the calculator should be used as part of a broader diagnostic workflow. Look at the numerical value, but also consider the patient's symptoms, respiratory rate, mental status, and other evidence of electrolyte abnormalities. A raised number may support systemic toxicity, while a borderline result may still be clinically important if the full picture suggests aspirin exposure.
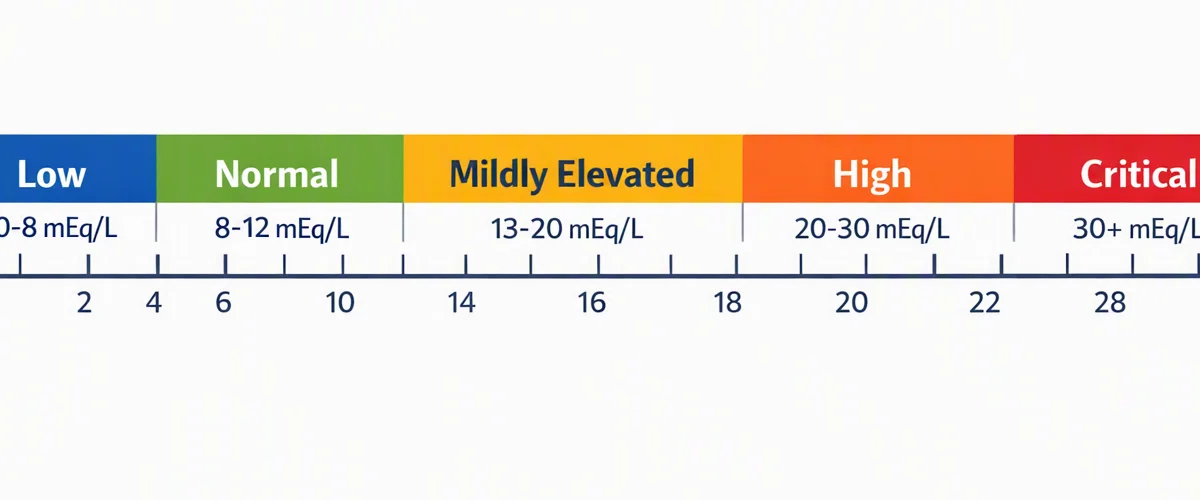
It is also important to compare the calculated result with the laboratory’s reference range if one is provided. Different institutions may use slightly different methods or reference values, which affects laboratory interpretation. The goal is not simply to identify an abnormal number, but to use that number to guide toxicology evaluation and further testing.
Classic Lab Patterns in Aspirin Toxicity
Aspirin toxicity typically presents with its combined and sometimes evolving lab profile. A common early pattern is respiratory alkalosis with a decreased or dropping bicarbonate, followed by metabolic acidosis as salicylate burden rises. This is why an arterial blood gas is especially useful. The arterial blood gas gives direct information about pH, carbon dioxide, and bicarbonate status, which helps confirm the presence of a mixed acid-base imbalance.
Patients with salicylate poisoning may show a reduced carbon dioxide level because of hyperventilation. At the same time as this, the bicarbonate may be reduced due to the metabolic component. The anion gap may increase as acids accumulate. This creates a diagnostic challenge: a patient can have roughly normal pH if respiratory alkalosis and metabolic acidosis counteract one another. That is one reason clinicians should avoid relying on pH alone when evaluating a potential toxic ingestion.
Lactate may also be elevated in aspirin toxicity. However, elevated lactate does not by itself explain the disturbance by itself. Salicylates can impair energy production and contribute to acid generation beyond simple tissue hypoperfusion. Therefore, lactate is a helpful part of the poisoning workup, but it should be interpreted together with the anion gap, arterial blood gas, and the rest of the clinical data.
Another key pattern is that the severity of symptoms does not consistently reflect the first available lab values. Early testing may miss the full metabolic derangement. Repeat assessment is often needed because the toxicology evaluation can progress swiftly. A patient may progress from a relatively subtle pattern to severe systemic toxicity over a short time.
Corrected anion gap and Albumin Adjustment
Albumin is the main not directly measured anion in the blood, so reduced albumin can make the anion gap value appear deceptively unchanged. This is particularly relevant in hypoalbuminemia, where the standard gap may understate the true burden of hidden acids. For that reason, a corrected anion gap is often more accurate when acid-base interpretation counts clinically.
In suspected salicylate poisoning, albumin adjustment helps keep from missing a hidden high-gap state. If albumin is decreased, the measured anion gap should be corrected before concluding that the serum chemistry is comforting. This step improves diagnostic accuracy and lowers the chance of false reassurance in a patient with possible toxic ingestion.
Corrected values are particularly useful when other findings point toward poisoning despite a slightly abnormal number. For example, a patient may have tachypnea, nausea, ringing in the ears, and an arterial blood gas showing mixed acid-base disorder, yet the initial gap is only mildly elevated. In that setting, albumin correction can expose a more meaningful abnormality and improve acid-base interpretation.
Albumin adjustment is not only about mathematics. It is about matching the laboratory pattern to the patient's physiologic state. In clinical practice, the corrected anion gap helps synthesize acid-base balance, serum chemistry, and toxicology evaluation so the clinician can identify systemic toxicity earlier.
When a Increased Anion Gap Raises Concern
A increased anion gap within the appropriate clinical context should prompt concern about a major underlying problem. In salicylate poisoning, this may suggest accumulated organic acids and disrupted metabolism. However, the differential diagnosis is wide, and the gap should call for a structured evaluation rather than an assumption of a cause.
Other common explanations include ketosis from diabetes, fasting, or alcohol-related conditions, and impaired kidney function, where acid clearance is impaired. A toxic exposure can also produce a high gap, including salicylates, methanol, ethylene glycol, or other agents. This is why the anion gap calculator is best used as a screening and triage tool within a larger diagnostic workflow.
When the gap is raised, ask whether the pattern matches the story. Does the patient have respiratory alkalosis and metabolic acidosis together? Are there symptoms that indicate aspirin exposure? Is there evidence of dehydration, reduced kidney function, or glucose abnormalities that might support another explanation? These questions strengthen clinical correlation and prevent misclassification.
The anion gap also matters because a rising value can signal increasing metabolic derangement. Even if the patient initially appears well, an increasing gap along with worsening symptoms may indicate advancing systemic toxicity. In that setting, repeat testing and rapid toxicology evaluation become even more essential.
Medical Follow-up Steps Following the Calculation of the Gap
Following calculation of the gap, the next move is to relate the result to the entire poisoning workup. If salicylate poisoning is suspected, obtain a salicylate level as soon as possible. This matters because the anion gap alone cannot quantify exposure or severity. A level helps establish the diagnosis, monitor trends, and direct treatment decisions.
Review the full set of electrolytes, including sodium, chloride, bicarbonate, potassium, and any other available serum chemistry markers. Electrolyte abnormalities are frequent in toxic states and can affect acid-base balance. If the patient is clinically concerning, a repeat blood gas and repeat chemistry panel may be needed to follow the course.
Repeat testing is particularly helpful when the presentation is early or unclear. Salicylate concentrations may rise after the initial sample if absorption continues, especially with enteric-coated products or delayed gastric emptying. The acid-base disorder may also evolve, shifting from mixed respiratory alkalosis and metabolic acidosis toward more severe acidemia.
Call poison control early when aspirin toxicity is possible. Expert guidance can help analyze the laboratory pattern, advise on follow-up testing, and support management decisions. Poison control is especially useful when the case interpretation is complicated by coexisting disease, uncertain timing, or ambiguous lab results.
At this stage, the key is bringing everything together. The anion gap calculator provides one data point, but toxicology evaluation depends on the whole picture: symptoms, lab trends, salicylate level, arterial blood gas findings, and the clinical course.
Limitations of the Anion Gap in Salicylate Poisoning
This anion gap has clear value, but it also has important drawbacks. A typical anion gap does not eliminate salicylate poisoning, especially in early poisoning or in patients with low albumin or mixed disorders that hide the expected finding. That is one of the most important reasons not to rely on the calculator alone.
False confidence can arise when clinicians anticipate a marked gap increase and overlook worrisome symptoms. During the initial phase, respiratory alkalosis may predominate, and the acid-base component may not yet be fully expressed. A patient can thus seem sick while the gap remains within normal limits or near normal. That is why the result must be read with clinical reasoning rather than used as a test to exclude it.
One more constraint is that acid-base assessment can be influenced by a coexisting illness. Renal impairment may change baseline chemistry. Ketone buildup can independently elevate the gap. Other metabolic disturbances can obscure the classic pattern of aspirin toxicity. In such cases, the gap remains helpful, but only as part of a wider toxicology evaluation.
The best use of the anion gap is as a useful clue for diagnosis. It helps detect hidden acids, aids in spotting mixed acid-base disorders, and prompts further evaluation. But it is not definitive. Good clinical judgment remains essential, especially when the presentation raises concern for systemic toxicity but the numbers are not straightforward.
FAQ About Anion Gap and Salicylate Toxicity
How does anion gap calculator help in salicylate poisoning?
A anion gap calculator helps by promptly revealing whether there is an unexplained increase in unmeasured acids, which can raise suspicion for salicylate poisoning. It is especially useful when used with serum chemistry, an arterial blood gas, and the clinical picture. In toxicology, it serves as an early diagnostic clue rather than a final answer.
Can salicylate poisoning occur with a normal anion gap?
Indeed. A normal anion gap value can be seen in early poisoning, in a mixed acid-base disturbance, or when reduced albumin masks the abnormality. This is why a normal finding should not create a false sense of security. If the medical history or signs suggest salicylate toxicity, additional testing and clinical correlation are still needed.
Why do patients with aspirin toxicity often have both respiratory alkalosis and metabolic acidosis?
Salicylates increase breathing, leading to respiratory alkalosis, while also altering metabolism and producing organic acids, which causes metabolic acidosis. This mix creates a mixed acid-base disorder that can be seen on the arterial blood gas and in the anion gap. The pattern is a hallmark of toxicology evaluation for salicylate exposure.
Should the anion gap be corrected for albumin in suspected poisoning?
Absolutely, especially if albumin is low. Albumin contributes to the unmeasured anions in blood, so hypoalbuminemia can hide a meaningful gap elevation. A corrected anion gap improves acid-base interpretation and reduces the chance of missing toxic ingestion.
What labs should be checked after finding a high anion gap in suspected salicylate toxicity?
Order a salicylate level, complete electrolytes, bicarbonate, kidney function, lactate, and an arterial blood gas. Follow-up testing may be needed because the pattern can change over time. If the case is concerning, contact poison control and continue the poisoning workup with careful clinical judgment.