How the Anion Gap Shows in DKA
The anion gap is a laboratory-derived value that helps identify the cause of metabolic acidosis. In diabetic ketoacidosis, it is particularly useful because it indicates the accumulation of acids that are not directly measured on a standard chemistry panel. This makes the anion gap a valuable diagnostic tool for identifying high anion gap metabolic acidosis.
An anion gap calculator estimates the difference between the major measured cations and anions in the blood. The result helps clinicians review serum chemistry data in the context of the patient’s acid-base balance. In DKA, the gap rises as ketones build up and contribute unmeasured anions to the bloodstream.
Because DKA is an acidotic state, the body typically shows a low bicarbonate level along with an elevated anion gap. That pattern reflects ketone accumulation and a wider metabolic derangement. The anion gap does not diagnose DKA by itself, but it helps confirm the diagnosis and tracks how the condition is evolving over time.
How to Operate an Anion Gap Calculator
An anion gap calculator relies on a few routine lab values from the electrolyte panel. You enter the serum sodium, serum chloride, and serum bicarbonate values, and the calculator follows the calculator formula to produce the result.
The basic workflow is simple:
- Collect the latest serum sodium value. Collect the serum chloride value. Collect the serum bicarbonate value from the serum chemistry panel. Add the values into the calculator. Examine the result alongside the rest of the laboratory results and clinical assessment.
This is important because DKA evaluation hardly ever depends on one number alone. The anion gap is part of a larger lab interpretation process that includes the patient’s symptoms, glucose level, ketone testing, pH, and treatment response. A calculator speeds up the math, but interpretation still needs clinical judgment.
Many clinicians rely on the result as a quick screen for metabolic acidosis and as a marker of resolution of acidosis during treatment monitoring. As the underlying ketoacidosis improves, the anion gap should trend toward normal and eventually show anion gap closure.
Anion Gap Formula and Normal Ranges
The classic anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
With this equation, the calculator determines the balance between measured ions in the blood. Sodium is the primary measured cation, while chloride and bicarbonate are the principal measured anions included in the calculation. Any additional acids in the blood are often represented indirectly as unmeasured anions.
The normal anion gap range differs a bit depending on the laboratory method and the reference range used by that lab. That variation is why it is important to view the number in context rather than rely on a single universal cutoff. A mildly different result may still be normal if the lab’s reference interval differs.
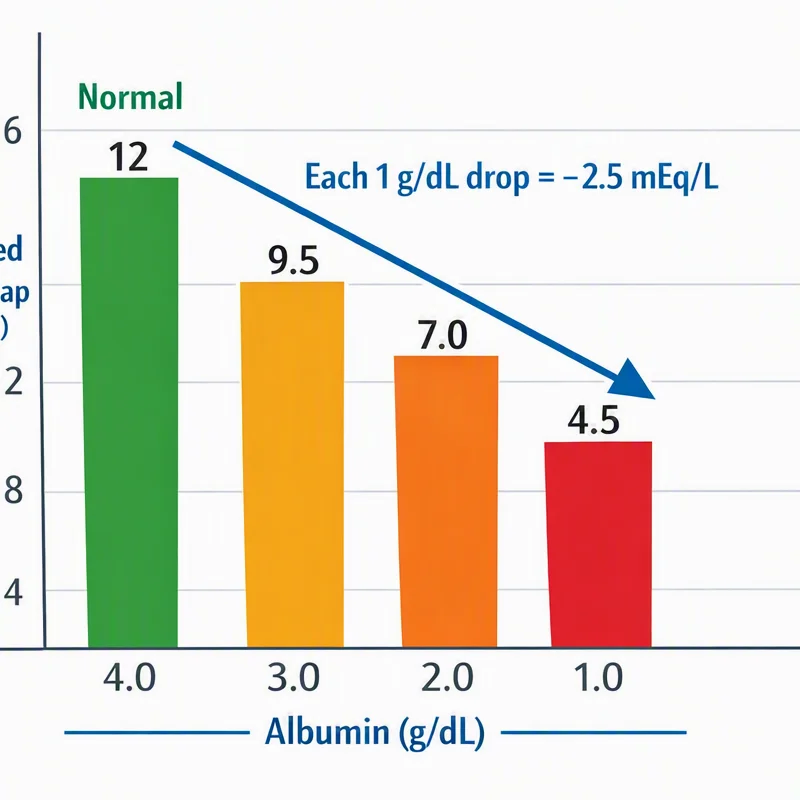
In practice, the anion gap should be considered with the rest of the electrolytes and with awareness of albumin correction. Albumin is a anion-like protein that affects the gap, so lower albumin can make the gap appear falsely low or normal. That is an important reason a raw value may not tell the full story.
Why the Anion Gap Is Raised in Diabetic Ketoacidosis
In DKA, reduced insulin leads to enhanced fat breakdown and production of ketones, notably acetoacetate and beta-hydroxybutyrate. These acids accumulate in the blood as unmeasured anions, which elevates the anion gap and drives ketoacidosis.
The process is a straightforward disturbance in acid-base balance. As ketones pile up, they consume bicarbonate, anion gap diabetic ketoacidosis lowering the bicarbonate level and resulting in a metabolic acidosis with a high anion gap. This pattern is a classic hallmark of DKA and helps distinguish it from other forms of acidosis.
Beta-hydroxybutyrate is commonly the dominant ketone in severe DKA, so the degree of ketosis may be more pronounced than a urine ketone test suggests. That is why the anion gap and direct ketone testing are complementary. Together, they reflect the patient’s acid burden more fully than either test alone.
Revising the Anion Gap for low albumin
Albumin strongly influences the measured anion gap because it is a important unmeasured anion in blood. When albumin is low, the anion gap may be too low. This is why albumin correction is often suggested, especially when the clinical picture suggests acidosis but the raw gap seems less striking than expected.
Hypoalbuminemia can occur in many hospitalized patients and can mask a true high-gap process. In that setting, a corrected anion gap gives a clearer picture of the patient’s metabolic state. The corrected value helps avoid missing DKA or underestimating the degree of acid accumulation.
Although formulas for albumin correction can vary slightly, the goal is the same: modify the gap based on the measured serum albumin so the value better reflects the true acid burden. This matters because a normal-looking gap can be deceptive if albumin is low. In DKA workups, the corrected value can improve lab interpretation and support more precise treatment monitoring.
Other Labs to Assess Together with the Anion Gap
The anion gap is only one part of the DKA workup. A careful evaluation also includes blood glucose, ketone body measurement, and acid-base testing. These studies help confirm the diagnosis and guide management.
An arterial blood gas or venous blood gas can reveal the pH and bicarbonate level, which indicate how severe the acidemia is. While venous testing is often adequate in many settings, the choice relies on the clinical context. Either way, the pH helps identify the acidotic state and supports the differential diagnosis.
Beta-hydroxybutyrate is especially useful because it directly measures ketone burden. It can demonstrate ketone accumulation even when other markers are less clear. Blood glucose is also essential, but a normal or only mildly elevated glucose does not rule out DKA, especially in euglycemic presentations.
Reviewing these findings together produces a more complete picture of the metabolic derangement. The anion gap, blood gas, glucose, and ketones should be considered as a group rather than as isolated laboratory results.
How the Anion Gap Changes During DKA Treatment
Management of DKA typically includes insulin treatment and intravenous fluids. As insulin inhibits ketone production and fluids support circulation and renal clearance, the anion gap should progressively fall. This trend is one of the strongest signs that treatment is succeeding.
During treatment monitoring, the clinician looks for anion gap closure, which suggests that the major ketoacid burden is clearing. The gap may normalize before the bicarbonate fully recovers, so it is important to look at the entire pattern rather than just one result.
Checking electrolytes is critical during this phase. Potassium, sodium, chloride, and bicarbonate can shift quickly as therapy progresses. IV fluids and insulin can also affect the apparent acid-base profile, so serial labs are needed to verify true improvement rather than a temporary lab shift.
As treatment continues, the goal is not only to lower glucose but also to correct the underlying acidosis. The anion gap helps show whether the ketoacid production has stopped and whether the body is progressing toward a stable acid-base balance.
Common Pitfalls and Assessment Errors
A typical error is not recognizing a combined acid-base disorder. A patient with DKA may also have nausea and vomiting, impaired respiratory compensation, or an additional metabolic issue that changes the expected pattern. In those cases, the anion gap may not tell the whole story by itself.
Laboratory error is another problem. A single incorrect sodium, chloride, or bicarbonate result can alter the calculated gap and lead to incorrect conclusions. If the number does not fit the clinical picture, it is wise to repeat testing and examine the full electrolyte panel.
Chloride-related acidosis can appear during or after DKA treatment, especially after large volumes of chloride-containing fluids. This can lower the bicarbonate while the anion gap normalizes, making the metabolic picture look unclear. In that setting, the persistent acidosis may be due to chloride rather than ongoing ketone production.
Serum albumin also matters here. If albumin is low and not accounted for, the gap may appear falsely reassuring. Careful lab interpretation requires awareness of the corrected value, the clinical assessment, and the treatment timeline.
When a Normal Anion Gap Is Not Enough to Exclude DKA
A normal anion gap does not definitively rule out DKA. One important example is euglycemic DKA, where the blood glucose may be normal or only mildly elevated despite active ketoacidosis. This can happen in certain medication contexts or with reduced carbohydrate intake, and it requires a high index of suspicion.
Another reason the gap may seem normal is that beta-hydroxybutyrate can remain elevated even when other markers are less dramatic. In early or partially treated disease, the anion gap may also begin to improve before the full metabolic picture resolves. That is why bedside assessment is so important.
If the patient still has symptoms and there is ongoing acidosis on blood gas testing, DKA can still be present even when the gap is not clearly elevated. In that setting, the differential diagnosis should include DKA, mixed disorders, and other causes of acidosis. The anion gap is valuable, but it is not a standalone rule-out test.
Common Questions
How is the anion gap related to diabetic ketoacidosis?
The anion gap in diabetic ketoacidosis is a computed lab measurement that helps detect increased anion gap metabolic acidosis. It increases because ketones build up as unmeasured acidic anions, decreasing bicarbonate and enlarging the gap. It is used to support diagnosis and follow improvement during treatment.
What is the calculation for the anion gap from lab results?
Apply the anion gap calculator or apply the calculation formula for the anion gap: sodium minus the sum of chloride and bicarbonate. The needed values are serum sodium, chloride level, and blood bicarbonate. Interpret the result together with the rest of the serum chemistry and clinical findings.
What is considered a normal anion gap range in adults?
A usual anion gap range depends on the laboratory’s normal range and testing method. Because ranges can differ, the best approach is to compare the result with the lab’s stated normal limits rather than using one universal number. Albumin level can also affect what looks normal.
What is the reason for correcting the anion gap for albumin?
The anion gap is corrected for the albumin level because low albumin can make the gap appear falsely low or normal. In hypoalbuminemia, the measured value may underestimate the degree of acidosis. Albumin correction helps produce a more accurate albumin-corrected anion gap for lab interpretation.
Can DKA occur with a normal anion gap?
Yes, it can. Euglycemic diabetic ketoacidosis, early treatment, low albumin, or a combined acid-base disorder can make the gap appear normal even when DKA is still present. If symptoms, ketones, pH, and bicarbonate suggest ongoing disease, the diagnosis should still be considered despite a normal gap.