What the Anion Gap Measures
The anion gap is a valuable clinical indicator that helps healthcare providers and patients review lab results as part of a broader assessment of acid-base balance. An anion gap calculator determines the gap between measured serum electrolytes in the blood chemistry panel, which reflects electrolyte balance and can point toward various acid-base disorders.
In simple terms, the anion gap compares the main positively charged and negatively charged ions reported on a routine electrolyte panel. The most important values are sodium, chloride, and bicarbonate. Because not all ions are directly measured, the anion gap can reveal whether there are other unmeasured acids in the bloodstream.
This makes the anion gap especially important in metabolic acidosis evaluation. A high result can suggest extra acid accumulation, while a normal result may indicate a different pattern of acid loss or compensation. The calculation does not stand alone, but it gives important context for clinical interpretation of the anion gap lab result.
Think of it as part of a broader serum electrolytes review. It is not a standalone diagnosis, but it can support the next steps in patient assessment and help rule out causes of abnormal blood chemistry.
How to Determine the Anion Gap
The typical anion gap formula relies on serum sodium, serum chloride, and serum bicarbonate. The usual version is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation estimates the difference between measured cations and anions. If you use an anion gap calculator, you simply enter the laboratory values from the basic metabolic panel or another electrolyte panel, and the tool produces the result right away.
Here is a straightforward example of how to calculate anion gap from lab results:
- Serum sodium: 140 Serum chloride: 102 Serum bicarbonate: 24
Using the formula: 140 - (102 + 24) = 14. That value may fall within a typical reference range, depending on the lab.
Some clinicians also use different formulas that include potassium, but the sodium-based version is the preferred for routine clinical interpretation. No matter the version, the goal is the same: to recognize patterns that may suggest metabolic acidosis or other shifts in acid-base balance.
Normal Anion Gap Range and Reference Values
The normal range for anion gap is influenced by the laboratory’s technique and reporting approach. That is why the exact lab reference range should always be reviewed alongside the result. Different analyzers, assays, and calculation methods can create lab variability.
In many settings, the usual range is narrow, but the acceptable value may differ based on whether potassium is included and whether the result is corrected for albumin. Because of this, a result that looks “high” in one lab may be considered acceptable in another. Always use the specific lab reference values associated with that report.
Albumin also matters because it is one of the major unmeasured anions in blood. When serum albumin is low, the measured anion gap can appear falsely unchanged or low, even when an acid-base problem exists. That is why interpreting the number without considering albumin can lead to overlooked results.
In short, the “normal” value is not just a fixed number. It is a situational result that must be interpreted with the lab’s stated reference range, the patient’s overall status, and other laboratory findings.
Adjusted Anion Gap and Adjustment for Albumin
Low albumin is one of the key factors to modify the anion gap. Because albumin contributes significantly to the unmeasured anions in blood, a low albumin level can lower the apparent gap. That is why albumin compensation becomes helpful.
The corrected anion gap helps compensate for reduced blood albumin. This adjustment enhances the accuracy of the result when evaluating possible metabolic acidosis. If the gap is not adjusted, a clinically important elevation may be missed.
A common approach is to use a correction factor when albumin is below normal. While formulas may vary slightly by institution, the goal is the same: approximate what the anion gap would be if albumin were normal. This makes the result more reliable for patient assessment and medical interpretation.
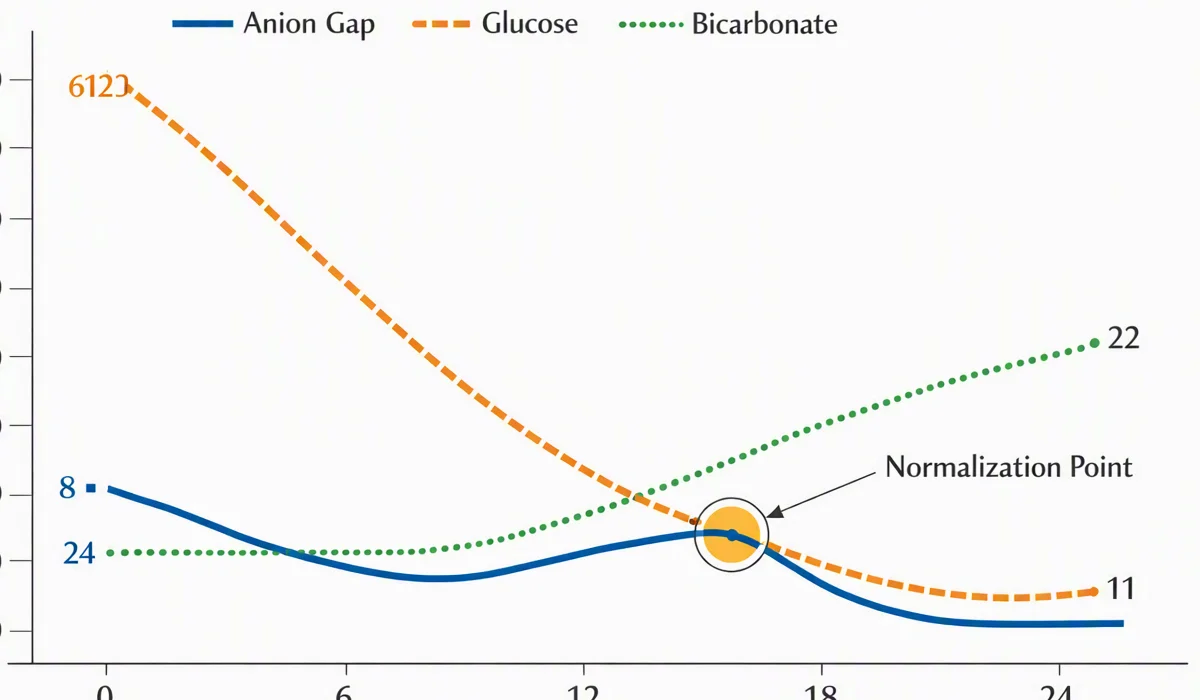
For example, a patient with low albumin may have an anion gap that appears normal, but after albumin correction, the value may suggest hidden elevated anion gap acidosis. In real-world practice, this is why albumin should be reviewed whenever the anion gap is used to interpret lab results.
When using an Anion Gap Calculator, look for a version that includes albumin adjustment or allows you to manually apply the correction. This is especially helpful in complex cases and in patients with chronic illness, malnutrition, or inflammation.
Elevated Anion Gap Compared with Expected Anion Gap Acidosis
A key point of the anion gap is telling apart high anion gap from normal anion gap acidotic states. Each are forms of metabolic acidosis, but they point to different mechanisms.
In elevated anion gap acidosis, acid anions accumulate in the blood. Common causes include lactic acidosis, ketotic acidosis, and renal dysfunction. These conditions raise acid production or limit acid clearance, which increases the gap.
In expected anion gap acidosis, the bicarbonate level drops but the gap remains within the normal range because chloride increases to maintain electrical balance. This pattern is often called chloride-associated acidosis. It is a distinct acid-base pattern from classic high gap states.
Understanding the difference helps direct the next steps in metabolic acidosis evaluation. A high gap suggests searching for acid accumulation or toxin exposure. A normal gap suggests considering bicarbonate loss, renal tubular issues, or other causes of acid-base imbalance.
The anion gap therefore works as a diagnostic marker that focuses the differential. It does not replace the full assessment, but it helps relate the numbers to the likely physiology.
Typical Causes of Unexpected Anion Gap Results
Abnormal anion gap results can suggest many disorders, and the most useful approach is to assess the patient context along with the laboratory findings. Common causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and uremia.
Lactate builds up when tissues are under stress and oxygen delivery or utilization is impaired. This can happen in severe illness, shock states, or other conditions that increase anaerobic metabolism. Elevated lactate is a typical cause of high gap acidosis.
Ketoacidosis occurs when ketone production builds, often in diabetes, prolonged fasting, or alcohol-related metabolic states. It can create a significant anion gap increase and should be considered when blood glucose or ketones are abnormal.
Renal failure can reduce the kidneys’ ability to clear acids, leading to uremia and accumulation of unmeasured anions. This is another classic cause of high gap abnormalities.
Other causes involve toxins and drug exposures. Salicylates can produce mixed acid-base findings and may elevate the gap. Other toxins can also contribute to an abnormal result, so history and medication review are important parts of the workup.
Because several conditions can overlap, the anion gap should be interpreted alongside symptoms, medication use, and the broader pattern of laboratory data.
How to Understand Outcomes With Other Lab Tests
The anion gap becomes much more useful when considered with other tests. A basic metabolic panel provides the core electrolyte values, but additional studies often clarify the cause of the abnormality and direct treatment decisions.
An arterial blood gas can show pH, partial pressure of carbon dioxide, and bicarbonate in more detail, helping define the type and severity of the acid-base disorder. A venous blood gas can also be helpful in many settings, especially when repeated monitoring is needed and arterial sampling is not necessary.
The osmolar gap is another key companion test when toxins or unusual ingestions are possible. A high osmolar gap may support concern for certain toxic alcohol exposures, while the anion gap may show concurrent metabolic changes.
When used together, these tests provide a structured clinical interpretation of acid-base balance. The anion gap helps identify unmeasured acids, the blood gas shows the physiologic effect, and the osmolar gap can point toward specific toxic causes. This combination improves the ability to rule out causes and determine whether the problem is a primary metabolic issue, a mixed disorder, or a compensatory response.
In real practice, the best results come from using the anion gap formula with the rest of the lab picture rather than viewing one number in isolation.
When to Get Medical Review
Certain anion gap findings need prompt review, especially when the result is paired with concerning symptoms or other abnormal labs. A markedly elevated or unexpected value may represent a critical problem that needs immediate attention.
Critical values should always be handled according to local lab policy and the patient’s condition. Even if the number is not formally flagged, a significant change from prior results can matter. Trend interpretation is often more informative than a single isolated number.
Seek urgent assessment when the abnormal result occurs with symptoms such as severe weakness, confusion, rapid breathing, vomiting, chest discomfort, or reduced consciousness. These findings may point to significant metabolic acidosis, toxic exposure, severe lactic acidosis, or another acute problem.
It is also important to use clinical judgment. The same anion gap value can mean different things in different patients depending on the reference range, albumin level, kidney function, and other laboratory findings. A number that seems mild in one case may be clinically important in another.
An anion gap calculator assists with decision-making, but it does not replace medical review. If the result is abnormal and the person is unwell, immediate evaluation is appropriate.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to determine anion gap values from lab results and help interpret lab results in the setting of acid-base balance. It is especially helpful in metabolic acidosis evaluation, where it can suggest whether the problem is likely to be a high anion gap state or a normal anion gap pattern. It also supports review of the anion gap lab result alongside the rest of the electrolyte panel.
How is calculated the anion gap from lab results?
Apply the anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, anion gap = serum sodium - (serum chloride + serum bicarbonate). This calculation uses values from the basic metabolic panel or another electrolyte panel and is the standard way to determine the result.
What is the normal anion gap range?
The normal range depends on the laboratory’s method and https://anion-gap-widget225.almoheet-travel.com/may-multiple-myeloma-lead-to-a-low-anion-gap reported lab reference range. Due to lab variability, always interpret the result with the specific report rather than relying on a single universal number. Albumin and whether the value is corrected for albumin can also influence interpretation, so the best answer always comes from the exact laboratory context.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because hypoalbuminemia can make the gap look artificially low or normal. Since serum albumin contributes to unmeasured anions, albumin correction improves accuracy and may reveal hidden acid accumulation. A corrected anion gap is especially useful when trying to identify occult high gap acidosis.
What does a high anion gap mean?
A high anion gap usually means there are extra unmeasured acids in the blood, which often points to metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and uremia. It can also be associated with salicylates or other toxins. The result should be interpreted together with symptoms, blood gas testing, and the rest of the laboratory findings for accurate clinical interpretation.