What the Anion Gap Measures
The anion gap is a simple way to examine the relationship between major electrolytes in the circulation and to help screen for metabolic acidosis. It contrasts the positive particles, especially sodium, with the main negatively charged particles, especially chloride and bicarbonate. Because not all charged substances are directly measured on a basic chemistry panel, the anion gap helps approximate the amount of unmeasured anions in the bloodstream.
In clinical practice, the anion gap is a helpful clue during serum chemistry review. It does not diagnose a condition by itself, but it can suggest an acid-base disorder that requires further evaluation. A high value may indicate excess acids in the blood, while a normal value can still represent a meaningful disturbance in acid-base balance.
Because the calculation uses standard blood chemistry results, it is often one of the earliest numbers clinicians use to interpret lab results. It can aid a focused clinical assessment of whether the patient has a true metabolic problem, a simple electrolyte pattern change, or a mixed disorder.
Think of the anion gap as a reliable diagnostic tool for identifying hidden contributors to metabolic derangement. When there is a mismatch between the measured cations and anions, the difference may suggest retained acids, changes in albumin, or another imbalance affecting overall chemistry.
How to Work With an Anion Gap Calculator
An anion gap calculator is meant to help you quickly calculate anion gap values from common lab findings. The calculator usually requires serum sodium, serum chloride, and serum bicarbonate. After inputting those laboratory values, the calculator uses the formula and displays the result for rapid review.
This is especially useful when you want to differentiate causes of a low bicarbonate or suspected acidosis. If the bicarbonate level is reduced, the anion gap can help clarify whether acids are increasing or whether bicarbonate is being lost and replaced by chloride.
To use the calculator accurately:
- Enter the current serum sodium value from the chemistry panel. Input the serum chloride value. Input the serum bicarbonate value. Review the result in the context of the patient’s symptoms and other laboratory values.
The calculator is not a substitute for a full diagnosis. Instead, it is a quick way to support a clinical assessment and identify whether the pattern fits a high gap acidosis or a normal gap acidosis. Because acid-base patterns can be mixed, the result should always be interpreted with the rest of the serum chemistry profile and the overall presentation.
Anion Gap Formula and Reference Ranges
The usual anion gap formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation estimates the separation between measured positive ions and measured anions. An elevated result suggests greater amounts of unmeasured anions are present. The precise normal range depends on the testing method and analyzer used, so the reported reference range from the lab should always be checked.
Many providers think of the normal range as a quite limited window, but it is important to use the range provided by the specific laboratory. A result that seems elevated in one setting may be considered normal in another if the lab method differs.
Albumin matters because it is a important negatively charged protein in blood and has a substantial effect on the measured gap. Since albumin is not always accounted for directly, low values can make the anion gap appear incorrectly normal or low. That is why the albumin-corrected anion gap can be more revealing when albumin is abnormal.
When using the formula as a screening tool, remember that the goal is not only to identify a number outside the normal range. The goal is to understand the pattern of acid-base balance and whether the numbers suggest a hidden cause of metabolic acidosis.
High Anion Gap Metabolic Acidosis
Elevated anion gap metabolic acidosis happens when acids build up in the body and raise the number of unmeasured anions. This is among of the most important uses of the anion gap because it aids in identifying reasons of serious illness that may require urgent treatment.
Common causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactate builds up when tissue oxygen delivery or utilization is reduced. In ketoacidosis, ketone bodies accumulate due to insulin deficiency, starvation, or another major metabolic stress. In renal failure, the kidneys cannot effectively eliminate acid loads, leading to retention of acids in the blood.
Other causes may also produce a high gap pattern, but these three are among the most clinically important. The anion gap helps identify a pattern that suggests the acidosis is not simply due to bicarbonate loss. Instead, it points to added acids that shift the chemistry profile.
A patient with metabolic acidosis and a high anion gap may also have tachypnea, nausea, altered mental status, or signs of systemic illness. The calculator can flag the abnormal pattern early, but the next step is to identify the cause through history, exam, and additional tests.
When the gap is elevated, it is helpful to ask whether the clinical picture fits a toxin exposure, shock state, diabetes-related crisis, or kidney dysfunction. This is where the anion gap becomes a useful screening tool rather than just a formula.
Normal Anion Gap Acidosis
Non–anion gap metabolic acidosis is also called normal anion gap metabolic acidosis. In this pattern, bicarbonate decreases, but chloride increases to maintain the gap within the normal range. That is why it is sometimes called hyperchloremic acidosis.
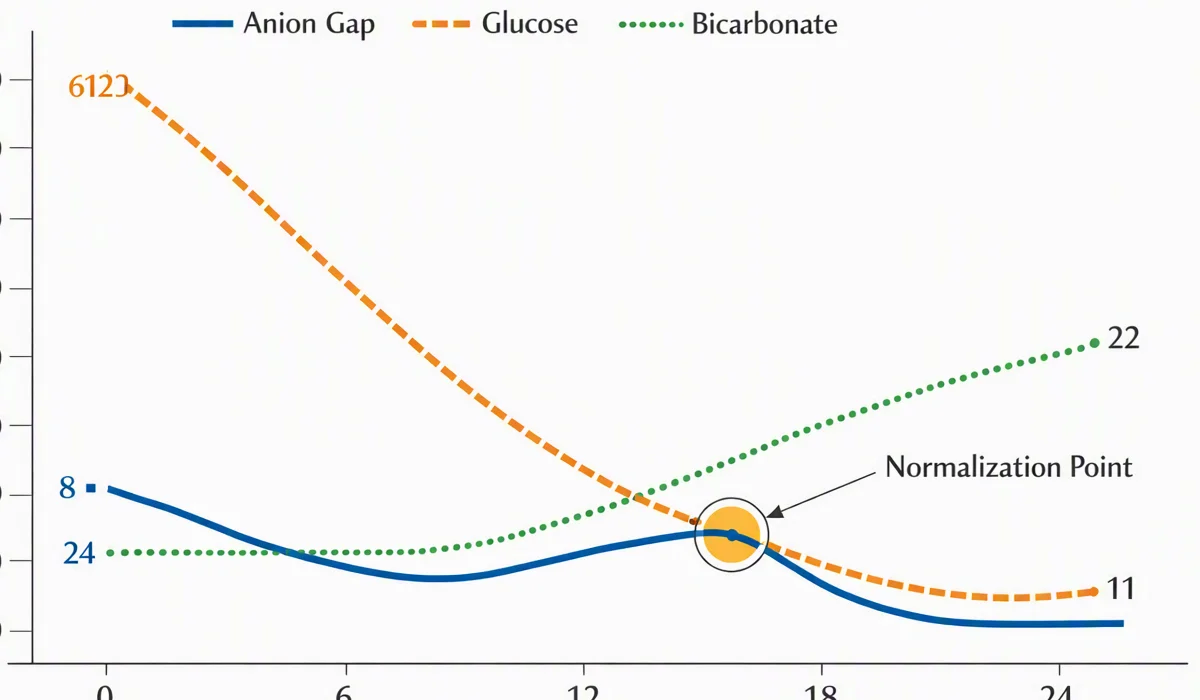
Common causes include diarrhea and renal tubular acidosis. In diarrhea, bicarbonate is lost from the gastrointestinal tract. With renal tubular acidosis, the kidneys do not properly acidify the urine or manage acid-base transport, which leads to persistent acidosis despite having a normal gap.
This finding is clinically important because a normal value does not rule out a meaningful acid-base disturbance. A patient can still have metabolic acidosis even when the gap is not elevated. The calculator helps reveal whether the low bicarbonate is being balanced by a rise in chloride, which is typical of this type of pattern.
Recognizing normal anion gap metabolic acidosis helps differentiate bicarbonate loss from acid accumulation. It also helps guide the workup on fluid loss, renal handling of acid, medication effects, or chronic disorders that affect electrolyte balance.
In short, a normal gap can still point to a serious acid-base disorder. The key is to interpret the result together with the bicarbonate level, the chloride trend, and the patient’s general clinical picture.
In What Way Albumin Affects the Anion Gap
Albumin acts as one of the primary contributors to the difference because it bears negative electrical charge in the bloodstream. When albumin is low, the overall amount of negative-charge-bearing measured anions falls, and the anion gap may seem smaller than expected. This is why hypoalbuminemia can obscure a important acidosis.
Albumin correction adjusts the result to more accurately reflect the real acid-base state. This is especially useful when albumin is out of range due to sickness, nutritional deficiency, inflammation, liver disease, or fluid overload. Without correction, a patient with an elevated acid burden may look to have a borderline normal gap.
The reason correction works is tied to protein charge. Albumin provides a significant portion of the negative charge in plasma, so changes in its concentration affect the balance between cations and anions. When albumin decreases, the apparent gap drops too, even if the underlying unmeasured anions are increased.
Using an albumin-corrected anion gap can increase diagnostic accuracy and help prevent missing a elevated-gap disorder. In clinical practice, if a patient has low albumin and a borderline anion gap, the corrected value may uncover an occult high anion gap metabolic acidosis.
For this reason, it is often advisable to correct for albumin whenever albumin is substantially reduced. This makes the anion gap more dependable as a screening marker and improves the interpretation of the serum chemistry panel.
Typical Causes and Medical Interpretation
Interpreting the anion gap takes more than determining whether it is high or normal. The result should be considered as part of the broader pattern of acid-base disorders. The best question is not just “Is the gap abnormal?” but “What type of disorder does this pattern suggest?”
Several common causes deserve special attention. Toxic alcohols can lead to a high-gap pattern because their metabolites anion gap in chronic kidney disease create Click here! acid and increase unmeasured anions. Salicylates may also lead to complex acid-base changes, sometimes with mixed respiratory and metabolic findings. Uremia, which reflects advanced kidney dysfunction, can cause acid retention and contribute to a raised gap. These conditions can be serious, so recognizing the pattern early matters.
During bedside assessment or in a chart review, the anion gap should be interpreted alongside symptoms, medications, renal function, and exposure history. A rising gap may point to worsening illness, while a low or normal result does not always mean the metabolic problem is gone.
Practical interpretation steps include:
- Examine the serum chemistry pattern for alignment with the reported bicarbonate and chloride values. Check for hypoalbuminemia and consider albumin correction. Determine whether the pattern fits high anion gap metabolic acidosis or normal anion gap metabolic acidosis. Search for clinical clues such as toxin exposure, kidney failure, GI losses, or insulin deficiency. Leverage the result to guide follow-up testing and treatment decisions.
This process helps turn a simple number into a important part of the diagnostic process. The calculator becomes a way to recognize patterns, refine the differential, and support timely management of an electrolyte imbalance or larger acid-base problem.
Common Questions
What is an anion gap calculator used for?
An anion gap calculator is used to derive anion gap values from routine lab results and assist screen for metabolic acidosis. It is a quick diagnostic tool for recognizing an acid-base disorder, especially when the goal is to identify a elevated-gap pattern or a normal-gap pattern that needs further interpretation.
How do you determine the anion gap from lab values?
Use the anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, anion gap = serum sodium - (serum chloride + serum bicarbonate). This formula relies on standard laboratory values from serum chemistry to calculate the amount of unmeasured anions.
What does a high anion gap mean?
A high anion gap typically suggests there are extra acids in the blood, which is why it is associated with high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. It can also occur with toxic alcohols, salicylates, or uremia.
Why is albumin correction important in the anion gap?
Albumin holds negative charge and strongly influences the gap. With hypoalbuminemia, the measured result may downplay the true acid burden. That is why albumin correction or the albumin-corrected anion gap is important for accurate interpretation, especially when trying to correct for albumin in a patient with suspected acidosis.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal value can still occur in normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern is often seen with diarrhea or renal tubular acidosis. So a normal gap does not exclude metabolic acidosis; it just suggests a different cause and pattern of acid-base balance.