What the Anion Gap Shows
The anion gap is a calculated value used in lab interpretation to help assess acid-base balance and recognize patterns that may point to a specific acid-base disorder. It is calculated from common electrolytes in the electrolyte panel, especially sodium, chloride, and bicarbonate. In practical terms, an anion gap calculator helps approximate the difference between measured positively charged and negatively charged ions, serving as a quick diagnostic aid for clinicians and lab readers.
The concept is based on electrical neutrality: the body’s fluids must keep a balance between cations and anions. Because some ions are not routinely measured, the anion gap reflects the presence of these unmeasured anions. This makes it a useful screening tool for metabolic conditions that alter serum sodium, serum chloride, and serum bicarbonate.
In everyday clinical interpretation, the anion gap is most often used to evaluate suspected metabolic acidosis. It can help differentiate high-gap acidosis from normal-gap acidosis, guide the interpretation of a broader metabolic derangement, and support faster lab result analysis. While the number itself is simple, its meaning depends on the full clinical picture, including the patient’s acid-base status.
How to Use an Anion Gap Calculator
An anion gap calculator usually needs three key lab values: sodium, chloride, and bicarbonate. These values are commonly reported on a standard metabolic panel or similar electrolyte panel. Once entered, the calculator uses the anion gap formula to calculate a result that can be compared with the expected reference range or reference interval.
To do it accurately, first confirm that the values are from the same sample and are current. Then enter the serum sodium, serum chloride, and serum bicarbonate exactly as reported. The calculator will subtract chloride and bicarbonate from sodium to estimate the gap. This is a simple approach to support clinical interpretation, but the result should always be reviewed alongside other labs and symptoms.
Because the anion gap is only one part of lab result analysis, it should not be interpreted in isolation. Changes in bicarbonate often reflect acid loss or acid buffering, while shifts in chloride may suggest compensatory changes. If the value is abnormal, the next step is usually to consider whether the pattern fits a metabolic acidosis, whether a corrected value is needed, and whether an arterial blood gas is available to clarify acid-base status.
Anion Gap Formula and Variants
The standard formula for the anion gap is:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians also include potassium in the calculation. With that approach, the formula becomes:
Anion gap = sodium + potassium - (chloride + bicarbonate)
The majority of modern laboratory systems and bedside references use the version without potassium because potassium is a smaller component of extracellular charge and adds little value in many routine settings. Still, understanding both forms can help when comparing historical reports or different clinical references.
This measurement is also influenced by albumin, which is a major negatively charged protein in plasma. Since albumin contributes to the measured gap, low albumin can make the result appear falsely low. That is why, albumin correction is important in many cases, especially when evaluating a patient with suspected acidosis or significant illness. A corrected anion gap can reveal abnormalities that a raw value might hide.
To put it simply, the anion gap formula is simple, but the interpretation is nuanced. A calculator helps speed up the arithmetic, while the clinician’s job is to decide whether the number is consistent with the overall acid-base picture.
Normal Anion Gap Intervals and Meaning
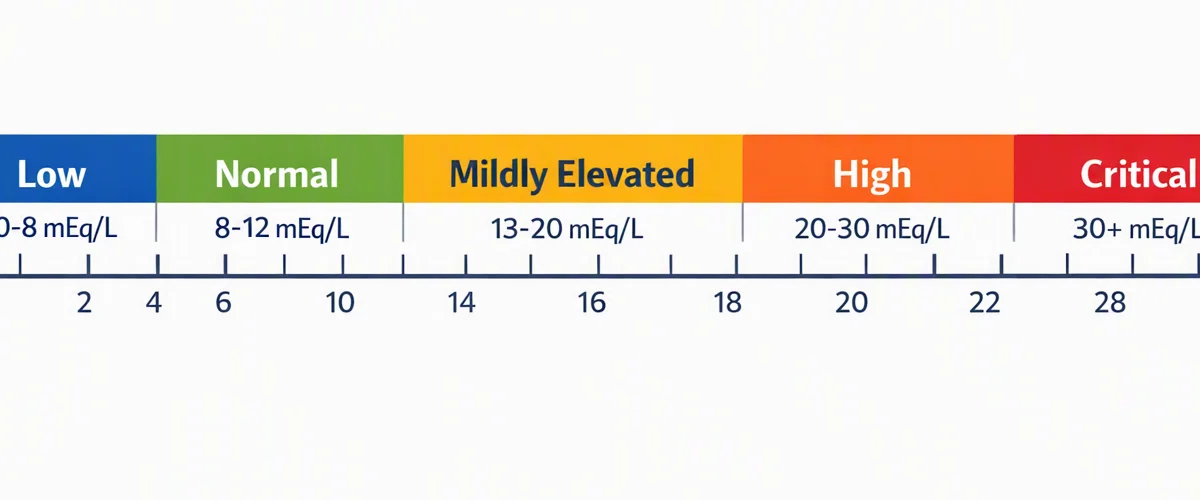
The usual reference range for the anion gap varies by laboratory method, analyzer, and whether potassium is included. This is why the site-specific reference interval is important more than any single universal cutoff. Many labs report a range that is more limited or broader depending on assay design, so the same result may be within range in one setting and near the limit in another.
A high anion gap suggests extra unmeasured acids in the blood, while a low anion gap suggests either a reduction in unmeasured anions, an increase in unmeasured cations, or a problem with the test itself. In real-world terms, the anion gap is a clue rather than a diagnosis. It helps frame the next steps in clinical interpretation.
Interpretation should also take into account the context of acid-base balance. A mildly abnormal value may be less concerning if other labs are stable, while a pronounced deviation may suggest a serious metabolic derangement. The same number can mean varied things depending on the patient’s hydration status, kidney function, and overall acid-base status.
For this reason, the anion gap is best viewed as a screening tool that supports broader decision-making rather than as a stand-alone result.
Reasons for Elevated Anion Gap
An increased anion gap often points to high anion gap metabolic acidosis, a pattern in which acids build up and widen the difference between measured cations and anions. Common causes include lactic acidosis, ketoacidosis, and renal failure. These conditions increase unmeasured anions, which elevates the calculated value.
Lactic acidosis happens when lactate builds up faster than it can be cleared, often in settings of poor perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis develops when ketone bodies build up, such as in uncontrolled diabetes, starvation, or alcohol-related metabolic stress. In both cases, the extra acid depletes bicarbonate, reducing serum bicarbonate and raising the gap.
Renal failure can also result in elevation because the kidneys cannot efficiently excrete acid load and metabolic byproducts. As kidney function worsens, retained acids contribute to metabolic acidosis. In real-world lab interpretation, this pattern may appear alongside changes in creatinine, blood urea nitrogen, and other markers of impaired clearance.
Other contributors to a high gap may include toxins or less common metabolic disorders, but the most frequent clinical causes remain lactic acidosis, ketoacidosis, and renal failure. An anion gap calculator can help identify the pattern quickly, but the next step is always to match the result with the patient’s symptoms and additional tests.
Reasons of Decreased Anion Gap
A reduced anion gap is uncommon and can be overlooked, but it may nevertheless be clinically relevant. A common cause is hypoalbuminemia, because albumin is a negatively charged protein that normally contributes to the gap. When albumin decreases, the anion gap may look diminished even if the patient has an underlying acid-base problem.
Paraproteinemia is an additional cause. In disorders that make abnormal proteins, the balance of measured and unmeasured ions can shift, decreasing the result. This is why a chronically low anion gap should prompt thought about protein abnormalities as well as the overall clinical context.
Laboratory error is also a common explanation. An unusual result should always raise the possibility of a specimen problem, analyzer issue, or transcription mistake. Because the anion gap depends on several measured values, a small measurement error in sodium, chloride, or bicarbonate can change the final number.
When the number is unusually low, it is useful to recheck the raw labs, review the reference interval, and consider whether hypoalbuminemia or paraproteinemia may explain the finding. In some cases, the apparent abnormality disappears once the data are rechecked or adjusted.
Corrected Anion Gap and Albumin Correction
The revised anion gap takes into account the effect of albumin on the measured result. Since albumin is a major unmeasured anion, low levels can mask a true elevation. That is why albumin correction is especially valuable in patients with low protein states, chronic illness, inflammation, or fluid overload.
A common correction formula adjusts the observed anion gap upward when albumin is below normal. While exact equations may vary by institution, the general idea is simple: lower albumin means a higher corrected value than the raw calculation suggests. This helps reveal hidden acid accumulation that might otherwise be missed during routine lab result analysis.
Hypoproteinemia can also affect interpretation, because the total protein environment shifts along with albumin. In such cases, a low uncorrected gap may not reflect true normality. The corrected value provides a more reliable picture of acid-base balance and supports more accurate clinical interpretation.
For patients with suspected metabolic acidosis and low albumin, correction is often essential. Without it, the clinician may underestimate the severity of a high-gap acidosis. The corrected value is not a replacement for the full evaluation, but it is a valuable step in interpreting the chemistry panel.
How to Interpret Findings in Acid-Base Disorders
The anion gap is especially helpful when considered alongside the broader assessment of acid-base disorder. In suspected acidotic metabolic state, the first question is whether the gap is elevated. If it is, the pattern suggests increased anion gap metabolic acidosis. If the gap is normal but bicarbonate is low, the pattern may fit non-anion gap metabolic acidosis, sometimes called non-gap acidosis.
An arterial blood gas helps confirm the pH, respiratory compensation, and overall acid-base balance. Together with the chemistry panel, it clarifies whether the problem is primarily metabolic, respiratory, or mixed. The anion gap does not replace the blood gas; it supports it.
The delta gap can be helpful when the anion gap is elevated. This approach compares the rise in the anion gap with the fall in bicarbonate to look for mixed disorders. If the change in one does not match the change in the other, a second acid-base process may be present. This is especially useful in complicated cases where more than one metabolic process is affecting the patient.
In practice, clinicians use the anion gap to move from methanol poisoning AG interpretation a general label like metabolic acidosis to a more specific working diagnosis. That is what makes it such a valuable piece of laboratory interpretation.
Frequent Mistakes in Anion Gap Interpretation
One of the most common pitfalls is depending on a single value without considering the full chemistry pattern. A result may appear normal despite a clinically significant problem if there is analytic error or if the laboratory’s reference range is different from the one used in a textbook. Make sure to check the lab’s own range before drawing conclusions.
Another issue is failing to account for undetected anions or protein changes. A low albumin level can hide a meaningful elevation, and a normal raw result may not fully reflect the patient’s acid burden. Likewise, paraproteins or other unusual proteins can distort interpretation.
It remains important not to mistake the anion gap with a diagnosis. The result suggests a pattern, but the cause must be identified through medical history, exam, and additional testing. Missing laboratory error can also lead to unnecessary concern or missed treatment.
Careful clinical interpretation means reviewing the full set of data: sodium, chloride, bicarbonate, potassium when relevant, albumin, kidney function, and blood gas findings. In this context, the anion gap is a useful guide; used in isolation, it can mislead.
FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used for clinical interpretation of electrolyte results. It helps analyze lab values from the chemistry panel to assess acid-base status, screen for metabolic acidosis, and identify patterns such as high anion gap metabolic acidosis or normal anion gap metabolic acidosis. It is a practical screening tool, not a diagnosis by itself.
How do you calculate the anion gap from lab values?
The basic anion gap formula is sodium - (chloride + bicarbonate). Some versions include potassium, but the classic formula usually does not. The calculator uses the reported serum sodium, serum chloride, and serum bicarbonate to produce the result. Always compare the value with the lab’s reference range.
What causes a high anion gap?
A high anion gap usually reflects extra unmeasured anions and is often seen in high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should be interpreted with the full clinical picture, including an arterial blood gas when available.
Why can a low anion gap happen?
A low anion gap can happen with decreased albumin, paraproteinemia, or lab error. Because albumin affects the gap, low protein levels may cause the value look lower than expected. If the finding is unexpected, recheck the test and check the rest of the lab values before thinking it is clinically meaningful.
When should albumin correction be applied to the anion gap?
Albumin correction should be considered when albumin is low or when a patient has suspected hypoproteinemia. In those cases, the uncorrected number may underestimate the true gap. A corrected anion gap gives a clearer estimate of the patient’s acid–base problem and can reveal hidden acid buildup.