What the Anion Gap Measures
The anion gap is a derived value that enables medical professionals and individuals determine whether the body’s body salts are in balance and whether an acid-base status problem may be evident. It does not detect a single substance directly. Instead, it calculates the difference between routinely measured positive and negative ions in the blood, which can point to clues about hidden acids or other unmeasured acids.
This anion gap calculator tool is a helpful clinical aid because it turns routine serum chemistry results into a helpful number for analysis. When the anion gap is beyond the expected range, it can indicate a acid-base imbalance, a different acid-base problem, or another metabolic abnormality that deserves closer evaluation.
The calculation is usually based on a standard blood electrolyte panel, especially the blood sodium level, chloride value, and blood bicarbonate level. These laboratory values offer a quick snapshot of the chemical environment in the bloodstream. Because the result is inferred, it should always be read in medical context, not as a stand-alone diagnosis.
How the Anion Gap Calculator Works
A tool that uses blood chloride input generally asks for the patient’s serum sodium, serum chloride, and serum bicarbonate. These three values are enough to calculate anion gap in the standard way. The calculator then calculates the gap between major measured cations and anions, which may indicate whether extra acids or other charged particles may be present.
In simple terms, the tool compares the sodium concentration against the combined effect of chloride and bicarbonate. For this reason the accuracy of the chloride level matters so much. If chloride is unusually high or low, the result can shift noticeably, sometimes changing the impression from a normal anion gap pattern to a high anion gap or the reverse.
This type of anion gap calculator is especially helpful when reviewing a serum chemistry report rapidly. It acts as a bridge between raw laboratory values and bedside reasoning, giving a prompt estimate that can support broader clinical decision-making. Still, the calculator is only one part of the assessment; the numbers must be matched with symptoms, history, and other laboratory values.
Method for Determining Anion Gap
The classic anion gap formula reads:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This equation relies on serum sodium as the principal measured cation and serum chloride plus serum bicarbonate as the main measured anions. The resulting difference indicates the balance of other ions not routinely measured in a basic panel.
Many clinicians rely on this value as a clue to the presence of unmeasured anions. For example, if the gap is elevated, it may suggest an accumulation of acids or acid-related substances. If the gap is lower than expected, it may reflect changes in albumin, chloride, or testing issues.
A calculator that uses blood chloride input is useful because chloride is a key variable in the equation. Even small changes in serum chloride can change the final result. That keeps the tool valuable for reviewing an electrolyte panel, confirming a suspected acid-base issue, or helping explain why two similar serum chemistry reports may produce different interpretations.
Normal Anion Gap Range and Assessment
The usual range for anion gap depends on the laboratory approach and the reference interval used by that lab. Different testing systems and measurement approaches may produce slightly different results, so there is no single universal cutoff that applies everywhere. That is why the reported normal range from the laboratory should always be checked first.
A normal anion gap generally suggests that the major measured ions are in normal balance and that no major accumulation of unmeasured acids is obvious from the calculation alone. However, a normal value does not automatically mean everything is normal. Some acid-base problems may still be present, especially if the pattern of sodium, chloride, and bicarbonate suggests another issue.
A elevated anion gap usually points toward additional acids in the blood, while a decreased anion gap is less common and may indicate changes in proteins, measurement issues, or unusual laboratory patterns. In all cases, the number should be interpreted alongside the patient’s symptoms, the electrolyte panel, and broader medical context.
How chloride entry Is Important
Blood chloride is not just a secondary value; it is essential to the calculation. Because chloride directly reduces the result in the anion gap formula, any drop or lowering in serum chloride can meaningfully affect the outcome. This is why an anion gap calculator that explicitly asks for chloride input can provide more useful insight than a basic explanation of the formula.
When chloride is elevated, a pattern called hyperchloremia may appear. This can reduce the calculated gap and sometimes hide a coexisting acid-base process. When chloride is reduced, or hypochloremia is present, the gap may increase or appear harder to interpret. These chloride-related shifts are a reminder that the calculator reflects a relationship, not an isolated disease diagnosis.
For this reason, reviewing the chloride value alongside sodium and bicarbonate helps clarify whether the result reflects true physiology or just a change in one component of the electrolyte panel. In practice, the chloride level often provides the hint that makes the interpretation clearer.
Typical Causes of an Elevated Anion Gap
A increased anion gap typically points to a accumulation of acidic substances that are not measured directly in the standard electrolyte panel. A common cause is lactate-related acidosis, which can occur when tissue oxygen delivery or utilization is impaired. In this setting, lactate increases and the anion gap rises as the body’s acid-base balance shifts.
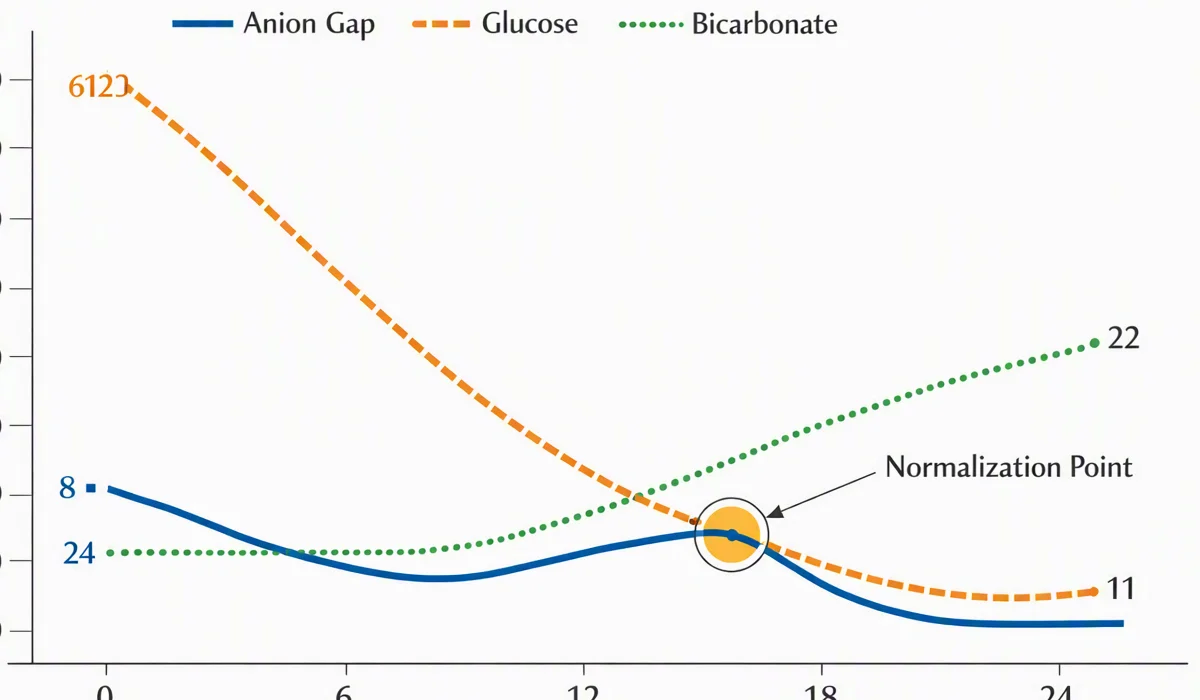
Another important cause is ketone-related acidosis. This may occur when the body produces excess ketones, which act as unmeasured acids. The calculator can help spot this pattern, but the result must still be paired with blood glucose, symptoms, and other findings. A growing gap in this context often reflects a significant metabolic disturbance.
Renal failure is also a classic cause of elevated gap values because the kidneys are less able to excrete acid and maintain normal electrolyte balance. As waste products accumulate, the anion gap may get higher. In these scenarios, the calculator is best used as an initial hint rather than a final answer.
Typical Causes of a Low or Unremarkable Anion Gap
A reduced anion gap is rarer than an high one, but it can be clinically important. One major cause is hypoalbuminemia, since albumin is a an anionic protein that helps maintain the normal gap. When albumin falls, the calculated number may drop even if there is an existing condition present.
Lab error should also be considered whenever the result seems not consistent with the clinical picture. Because the anion gap depends on several reported values, small problems in sodium, chloride, or bicarbonate reporting can shift the final value. That is why repeat testing or confirmation may be appropriate when the number does not fit the patient’s condition.
Multiple myeloma can occasionally produce a low anion gap because abnormal proteins may affect the balance of charged particles in the blood. This is another example of why the result should be read as part of a larger evaluation rather than as a standalone screening test.
How to Interpret Results in Perspective
Careful interpretation starts with the raw numbers, but it does not end there. The most practical approach is to compare the result against the laboratory’s reference range, evaluate whether an acid-base disorder is present, and then review whether the pattern suggests a true metabolic acidosis or another imbalance.
Albumin correction is especially important when serum albumin is low. Since albumin contributes to the normal measured gap, a patient with hypoalbuminemia may appear to have a normal or low result even if hidden acids are present. A corrected anion gap can provide a more accurate estimate of the underlying acid-base status in such cases.
The most helpful approach is to combine the calculator result with the patient’s symptoms, history, and other laboratory values. That is the essence of clinical correlation. A number that looks only mildly abnormal may be significant in one setting and less important in another. Likewise, a “normal” value may not exclude an evolving condition if the rest of interpret anion gap the acid-base picture suggests a problem.
Limitations of an Anion Gap Calculator
Even a carefully built anion gap calculator has limits. The result depends on the lab’s reference range, which can vary based on analyzer type and reporting method. Different institutions may also define the normal window differently, so the same numeric result may be interpreted differently across settings.
Lab variability is another major issue. Small changes in how sodium, chloride, or bicarbonate are measured can affect the final answer. Because the formula subtracts two values from sodium, tiny analytical differences can have a noticeable effect. This is especially relevant when the result is close to the upper or lower limit of normal.
Measurement error can also create misleading results. A sample problem, analyzer issue, or transcription mistake may make the gap appear abnormal when it is not. For that reason, the calculator should be viewed as a starting point for interpretation, not as definitive proof of disease. It is a helpful tool, but it cannot replace expert review of the full electrolyte panel and the patient’s clinical context.
Frequently Asked
How do you determine an anion gap using blood chloride?
To determine the anion gap using blood chloride, follow the standard anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. An anion gap calculator performs this calculation automatically once you enter the serum sodium, serum chloride, and serum bicarbonate values from the electrolyte panel. The result helps assess the balance of electrolytes and can aid in assessing an acid-base problem.
What is a high anion gap a sign of?
A high anion gap usually indicates there are additional acids or other unmeasured anions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. It is often a clue to metabolic acidosis, but the result should always be interpreted with the complete patient picture, not in isolation.
Can a normal anion gap still indicate a problem?
Yes. A normal anion gap does not completely rule out disease. Some acid-base disorders may still be present even when the calculated value falls within the expected reference interval. For example, changes in chloride, bicarbonate, or albumin can affect interpretation. That is why the electrolyte panel and overall clinical context matter.
Why does albumin affect the anion gap?
Albumin is a major negatively charged protein in the blood, so it contributes to the normal anion gap. When albumin is low, the gap may appear lower than expected even if an acid-base disorder exists. This is why albumin correction and attention to serum albumin are important when reviewing results, especially in hypoalbuminemia.
When should an anion gap result be repeated or confirmed?
A result should be repeated or confirmed when it does not match the patient’s condition, when there is concern for lab error or measurement error, or when the value is borderline and affected by lab variability. Confirmation is also reasonable if the result is unexpectedly high, low, or inconsistent with other laboratory values. In those situations, reviewing the full electrolyte panel and repeating the test can improve confidence in the interpretation.