What an Anion Gap Calculator Calculates
An anion gap calculator is a practical diagnostic tool used for estimating the difference between commonly measured electrolytes in blood. The calculated anion gap helps doctors evaluate electrolyte balance and refine the differential diagnosis of acid-base disorders, especially when evaluating metabolic acidosis.
The calculation relies mainly on sodium, chloride, and bicarbonate. These values come from routine lab values on a chemistry panel, and the result indicates the balance between measured ions and unmeasured ions or unmeasured anions in the blood. Because the body must maintain tight acid base balance, a change in the gap can signal a metabolic derangement that warrants closer evaluation.
At a basic level, the anion gap is not a direct measurement of acid. Instead, it is a screening estimate that helps detect whether extra acids or other charged particles are present. A rising gap may point to accumulation of acids, while a low gap can point to albumin changes, lab issues, or unusual cation excess. Used correctly, the calculator supports clinical assessment and more targeted interpretation of a patient’s chemistry profile.
In most settings, the calculator draws from serum sodium, serum chloride, and serum bicarbonate to support rapid bedside reasoning. That makes it especially useful when reviewing a serum chemistry panel in the context of acidemia, alkalemia, or a suspected compensatory response.
Anion Gap Formula and How It Is Calculated
The formula for anion gap is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
This straightforward formula matches the main measured cation, sodium, with the major measured anions, chloride and bicarbonate. Different laboratories may use other conventions, but this is the most familiar version and the one many clinicians use for initial review.
To use an anion gap calculator, start with the serum chemistry panel. Identify the sodium, chloride, and bicarbonate values. Then use the equation one step at a time:
- Record the sodium value. Add the chloride and bicarbonate values together. Take away that sum from sodium. Compare the result with the lab’s reference interval.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the gap is 140 − (104 + 24) = 12. That result is often in the normal range, though the exact reference range depends on the lab.
The calculation is helpful because it turns routine electrolyte data into a clue about hidden acids or shifted ions. In a patient with suspected acid-base disturbance, the gap may reveal whether the problem is associated with excess unmeasured anions or with bicarbonate loss and chloride retention. In that sense, the calculator is less about arithmetic and more about recognizing clinical patterns.
Normal Anion Gap Range and Assessment
The usual range for anion gap varies by device and method, so the most important reference is against the local laboratory reference range. A value that seems high in one lab may be normal in another. This is why anion gap results should always be viewed in context rather than in isolation.
A high anion gap usually suggests the presence of extra acids or other unmeasured substances that widen the gap. A decreased anion gap is less common and often suggests hypoalbuminemia, lab variation, or unusual ionic states rather than a primary acid-base problem.
Analysis depends on the entire biochemical picture. For example, a borderline result in a stable patient may not be meaningful, while the same value in someone with vomiting, altered mental status, or shock may be a critical clue. The calculator is therefore best viewed as part of broader clinical assessment, not a stand-alone answer.
Remember that the anion gap is influenced by the concentration of negatively charged proteins, especially serum albumin. Since albumin contributes substantial negative charge under normal conditions, a low albumin level can make the gap look falsely normal or low. That is one reason the raw number should always be read alongside the broader acid-base picture.
How the Anion Gap Helps Identify Acid-Base Disorders
The anion gap is most valuable when evaluating acid-base disorders, particularly when the question is whether metabolic acidosis is present and what type it may be. Practically speaking, it helps tell apart acid gain disorders and bicarbonate loss disorders.
In high anion gap metabolic acidosis, the body builds up acids that are not directly measured on the chemistry panel. These acids contribute to the gap because bicarbonate drops as it buffers excess hydrogen ions, while chloride may not rise enough to fully compensate.
In normal anion gap metabolic acidosis, bicarbonate is lost and chloride rises in a compensatory pattern. The measured gap can still appear normal even though the patient is anion gap in chronic kidney disease clearly acidotic. This is why the anion gap calculator is so useful: it helps identify different metabolic patterns that can look similar on first inspection.
The gap can also be informative in mixed pictures involving respiratory alkalosis. For example, a patient may hyperventilate and lower carbon dioxide while also developing metabolic acidosis. In that setting, relying on one number can create a false sense of clarity. Careful analysis of pH, bicarbonate, and the anion gap helps detect a mixed disorder.
Overall, the calculator supports a structured approach to acid base balance. It helps clinicians move from a single abnormal lab result to a more complete interpretation of the underlying physiology.
Increased Anion Gap Metabolic Acidosis Causes
An elevated gap suggests extra acids or retained acid equivalents. The classic causes include lactic acidosis, ketoacidosis, renal failure, and consumption of toxic alcohols. Each of these conditions increases the amount of unmeasured acid in the blood and shifts the biochemical profile away from normal.
Lactic acidosis occurs when lactate production exceeds clearance, commonly in cases of tissue hypoperfusion, sepsis, severe exertion, or impaired metabolism. Because lactate is an unmeasured anion in routine chemistry, it can elevate the gap significantly.
Ketoacidosis is another leading cause. It may occur in diabetes, prolonged fasting, heavy alcohol use, or other states of carbohydrate deprivation. Ketone bodies such as beta-hydroxybutyrate and acetoacetate add to the rise in the gap and often accompany symptoms of dehydration, nausea, and altered mental status.
Renal failure can elevate the anion gap because the kidneys are unable to excrete acid effectively. As acids build up, bicarbonate drops and unmeasured acids increase. This creates a metabolic pattern that commonly indicates advanced disease or acute decline.
Toxic alcohols like methanol and ethylene glycol can also produce a high gap. These agents are converted into acidic compounds that cause major metabolic derangement. In the appropriate setting, this pattern is a medical emergency and warrants immediate evaluation.
Even though the anion gap does not identify the exact toxin or acid, it is a powerful clue that guides further testing and treatment. That is why it is often one of the first numbers reviewed in suspected poisoning or unexplained acidemia.
Normal Anion Gap Acidosis with Normal Anion Gap Causes
A normal anion gap does not rule out acidosis. In normal anion gap metabolic acidosis, the key issue is often depletion of bicarbonate rather than accumulation of a new acid. The gap stays stable because chloride rises as bicarbonate falls, preserving the body's charge balance.
Typical causes include diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. This pattern is often called hyperchloremic acidosis because chloride increases as bicarbonate decreases.
Diarrhea can cause substantial gastrointestinal bicarbonate loss, especially when persistent or severe. The kidneys may attempt to compensate, but the chemistry panel often shows low bicarbonate and high chloride with a near-normal anion gap.
Renal tubular acidosis refers to impaired renal handling of acid or bicarbonate. Depending on the subtype, the kidneys may fail to acidify urine properly or may waste bicarbonate. Either way, the result can be ongoing metabolic acidosis with a normal gap.
Other settings can mimic this pattern, including some IV fluids, chronic kidney conditions, and mixed metabolic states. This is where careful interpretation matters: a normal gap should not stop the evaluation if the patient has a clearly low bicarbonate or a clinical picture consistent with acidosis.
The practical takeaway is simple: if the chemistry panel shows metabolic acidosis but the gap is not elevated, think about bicarbonate depletion, chloride retention, and causes of hyperchloremic acidosis before assuming the problem is mild or resolved.
Accounting for the Anion Gap for Albumin
Because albumin is a key negatively charged protein in plasma, low albumin can hide a true rise in the anion gap. This is why albumin correction is an integral part of modern interpretation. Without it, a patient with significant acid accumulation may appear to have a normal result.
The corrected anion gap refines the measured value to account for hypoalbuminemia. The exact correction factor may change slightly by formula, but the principle is the same: when albumin is low, restore a portion of the missing negative charge to approximate the true gap more accurately.
This matters because albumin contributes to protein binding and overall charge balance. If albumin falls, the measured gap may decrease even when unmeasured acids are present. In that situation, a seemingly normal anion gap may hide a clinically important high-gap process.
Albumin correction enhances interpretation in patients with liver disease, malnutrition, critical illness, or inflammation, where hypoalbuminemia is common. It is especially useful when evaluating possible lactic acidosis, ketoacidosis, or toxin exposure in a patient whose chemistry panel does not appear striking at first glance.
In practice, the corrected value should be considered alongside pH, bicarbonate, and the rest of the electrolyte profile. The goal is not just to calculate a number, but to avoid missing a serious acid-base disorder because of altered protein levels.
Typical Limitations and Limitations
Although the anion gap calculator is useful, it has limitations. One of the most common issues is lab error. A hemolyzed sample, transcription problem, or analyzer variation can distort the result. When the number does not match the clinical picture, repeating the test is often the best first step.
Another limitation is the presence of unmeasured cations. Substances such as lithium, severe magnesium elevation, or other cation excesses can lower the gap and obscure interpretation. Some medications may also alter acid-base status directly or indirectly, making the chemistry pattern less clear.
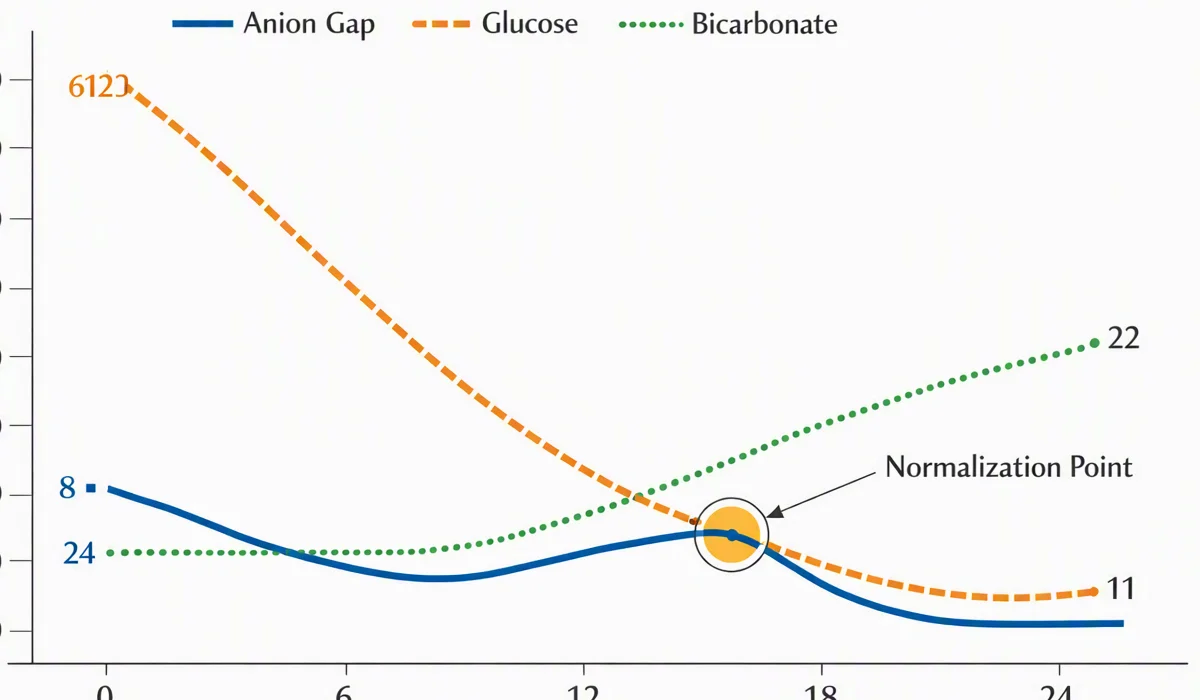
Assessment issues commonly occur when providers focus on the anion gap alone and neglect the complete acid–base context. The gap should be interpreted with pH, bicarbonate, carbon dioxide, and the patient’s clinical status. Otherwise, a mixed disorder or compensatory response may be undetected.
One more pitfall is overlooking that a “normal” result depends on the local reference range. A value may be abnormal relative to one measurement and acceptable in another assay. That means any reading should be assessed using the lab’s own reference range rather than an assumed universal cutoff.
Ultimately, the anion gap does not identify the cause by itself. It is a clue, not a medical diagnosis. Proper use requires relating the number to the broader context anion gap interpretation flowchart of electrolyte balance, clinical findings, and likely exposures. That combination is what makes the calculator clinically useful.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to evaluate acid-base disorders, notably metabolic acidosis. It helps clinicians determine whether the problem is more in line with a high-gap process such as lactic acidosis or ketoacidosis, or a normal-gap process such as diarrhea or renal tubular acidosis. In that manner, it aids clinical use as a quick triage and analysis tool.
How do you calculate the anion gap from lab values?
Apply the anion gap formula: sodium minus the sum of chloride and HCO3. That is, anion gap = sodium − (chloride + bicarbonate). This value comes straight from a serum chemistry panel and is among the most common forms of gap calculation in everyday practice.
What is a elevated anion gap mean in acid base disorders?
A elevated anion gap usually means there are additional unmeasured anions or hidden acids in the blood. When there is metabolic acidosis, that frequently suggests lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. It is an useful clue in acid-base assessment, but it still requires clinical correlation.
Why is the anion gap corrected the anion gap for albumin?
You adjust for albumin because reduced albumin can artificially reduce the measured gap. With albumin correction, the corrected anion gap gives a better picture of the true acid-base status, especially in hypoalbuminemia. This helps avoid missing a clinically important disorder when the raw value looks normal.
What causes a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is commonly caused by diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. It is often described as hyperchloremic acidosis because chloride rises as bicarbonate falls. If the bicarbonate is low but the gap is not elevated, these causes should be part of the diagnostic workup.