What Is the Anion Gap?
The anion gap is a computed value that helps assess acid-base status by comparing the main measured electrolytes in a blood sample. It is typically calculated from a serum chemistry panel or other serum electrolytes results, using the relationship between sodium, chloride, and bicarbonate. Clinically, it can identify whether there are unmeasured anions contributing to an anion deficit and an underlying acid-base disorder.
In simple terms, the anion gap is a diagnostic tool that measures the difference between positively charged and negatively charged particles in the blood. That difference reflects electrolyte balance and can point anion gap in chronic kidney disease to a metabolic disturbance that is not obvious from the individual values alone. Because it is based on routine blood chemistry, it is often used as a screening test during patient assessment.
Most modern labs provide the ingredients needed for the calculation as a standard laboratory result. Even though the concept sounds abstract, the practical use is straightforward: if the gap is elevated, clinicians think about causes of metabolic acidosis, especially high anion gap metabolic acidosis.
Anion Gap Calculation Formula Without Potassium
The most commonly used calculation method without potassium is:
Anion gap = sodium - (chloride + bicarbonate)
This method uses sodium value, chloride value, and bicarbonate level values from the lab. If you're using an Anion Gap Calculator, this is generally the default method because it is more straightforward and aligns with common clinical practice.
The values are usually reported in mEq/L. The formula subtracts the sum of chloride and bicarbonate from sodium. Since sodium is the principal measured cation in the panel, and chloride plus bicarbonate are the principal measured anions, the result estimates the space left by negative charge from unmeasured substances.
Although some older formulas also included potassium, many clinicians omit it because the contribution is small and does not usually change the practical clinical interpretation. A simplified formula makes the calculation simpler without sacrificing much utility in routine use.
If you check the result manually, make sure the units match and that the numbers come from the same lab values set. An error in units or transcription can affect the result significantly.
Step-by-Step Calculation Demo
This is a straightforward sample calculation using standard test values:
- Sodium = 140 mEq/L Cl = 102 mEq/L HCO3 = 24 mEq/L
With interpretation of anion gap values the equation:
Anion gap = 140 - (102 + 24)
First combining chloride and bicarbonate:
102 + 24 = 126
Then subtract from sodium:
140 - 126 = 14
This anion gap result is 14 mEq/L. According to the laboratory reference range, this may be considered normal or mildly elevated. That is why the result must always be interpreted in context rather than as a stand-alone number.
Relying on an anion gap calculator can minimize arithmetic mistakes, but the manual method is easy to check. The key is to remember the exact formula and to use current lab values rather than outdated results. When values change rapidly, the gap can shift along with the patient’s acid-base status.
Typical Range and Meaning
A typical anion gap depends on the laboratory reference interval, the analysis method, and whether potassium is included. In numerous labs, a typical non-potassium result is roughly in the low teens, but the exact normal interval changes from one lab to another. Always review the number with the lab’s stated range instead of relying on a universal cutoff.
A raised anion gap suggests extra unmeasured acids in the blood. This pattern is commonly associated with acidosis, especially elevated anion gap metabolic acidosis. The finding can help narrow the differential diagnosis, but it does not identify the cause by itself.
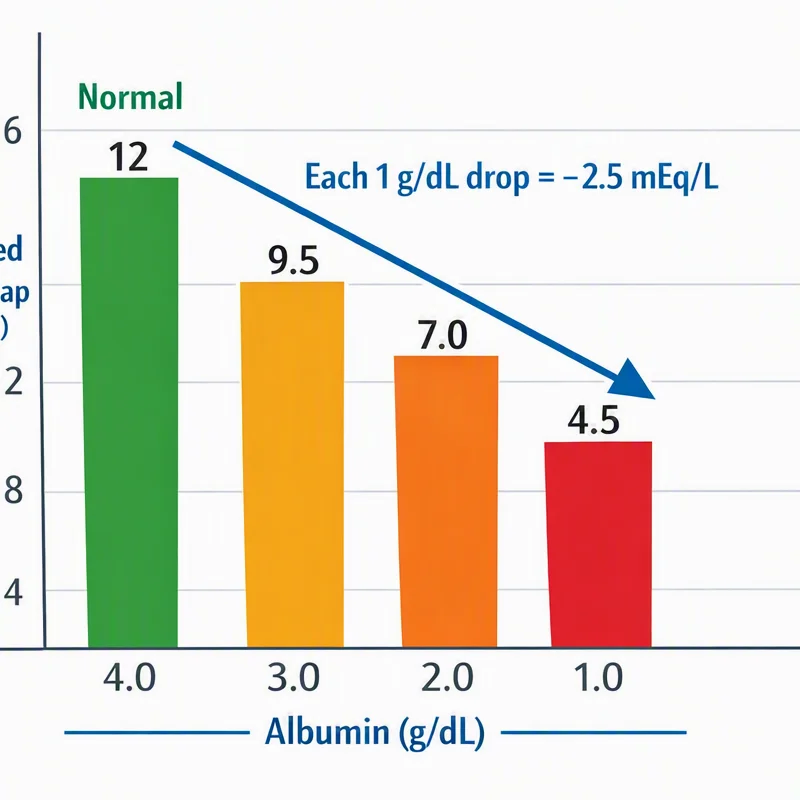
One important factor is albumin. Because albumin is a major unmeasured anion, low albumin can make the anion gap appear lower than expected. In those cases, clinicians may use an corrected anion gap to get a more precise adjusted value. This is especially useful when evaluating a suspected acid-base disorder in patients with hypoalbuminemia.
Interpretation should also distinguish high-gap from normal-gap metabolic acidosis. A normal gap does not rule out acidosis; it may indicate bicarbonate loss with a compensatory rise in chloride, as seen in normal-gap patterns. That is why the number should always be read alongside the full chemistry panel and the broader clinical picture.
The reason Potassium Is Often Excluded
Potassium is often excluded because its concentration is far lower than sodium, and the difference usually has little impact on everyday clinical practice. The simplified formula enhances consistency and accelerates use in busy settings. Many forms of laboratory reporting also omit potassium for this reason.
From a practical standpoint, leaving potassium out makes the calculation simpler to recall and reduces the chance of error. The change in result is typically slight enough that it does not change the general conclusion, especially when the goal is early screening rather than highly specialized analysis.
That said, the omitted-potassium method is not a different concept. It is the same physiologic idea, just a streamlined approach built into many calculators and lab systems. If an older source includes potassium, the resulting number will be a bit higher, but the overall assessment of acid-base status often stays similar.
In other words, the anion gap calculator commonly used in practice is based on the simplified formula because it is practical, consistent, and appropriate for most patient assessment scenarios.
Origins of a Increased Anion Gap
A elevated result indicates additional acid or undetected anions in the bloodstream. Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Each of these can elevate the gap for a distinct reason, but all lead to an build-up in hidden acids.
Lactic acidosis develops when lactate builds up, often in settings of reduced perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis occurs when ketones rise, such as in diabetes or prolonged fasting. Renal failure can limit acid excretion, permitting acids to build up. Toxic ingestions may expose the body to substances that are metabolized into acids or that interfere with normal metabolism.
These causes are especially important important when the anion gap is elevated with signs of metabolic acidosis. A clinician may view the gap as a clue, then combine it with history, physical findings, and additional testing to find the underlying problem. The gap itself is a clue, not a final diagnosis.
Because different disorders can produce the same pattern, the value should be considered part of a wider diagnostic framework. A patient with high-gap acidosis needs a focused evaluation, and the anion gap calculator can help flag the issue early.
Drawbacks of the Anion Gap Calculator
An anion gap calculator is valuable, but it has significant drawbacks. The primary is correction for albumin. Since albumin is a primary contributor to the normal gap, low albumin can hide a significant elevation. When uncorrected, the result may look misleadingly normal.
Also, the result is affected by the testing facility’s reference range. Various methods, machines, and reporting practices can produce different numbers, so a result that seems unusual in one lab may be appropriate in another. For this reason interpretation should always be tied to the local laboratory’s reference interval.
Third, lab error may distort the outcome. Contaminated samples, late analysis, or recording mistakes can affect sodium, chloride, or bicarbonate values. Since the gap is computed from these values, even one inaccurate lab result can lead to a incorrect conclusion.
Finally, the result is only one part of the evaluation. It does not take the place of a complete clinical assessment, arterial or venous blood gas when needed, or evaluation for other causes of acid-base disturbance. When used correctly, it is a useful screening measure; by itself, it can be limited.
Common Questions
How do you calculate anion gap without potassium?
Use the formula the formula sodium - (chloride + bicarbonate). This is the common simplified approach and is what what most anion gap calculator resources use. Type in the lab values in mEq/L and deduct the sum of chloride and bicarbonate from sodium.
Can you explain the formula for an anion gap calculator without potassium?
The equation is anion gap = sodium - (chloride + bicarbonate). It relies on the main serum electrolytes from the lab panel and excludes potassium for clarity. This serves as the most common calculation formula in daily practice.
What is a usual anion gap excluding potassium?
The expected values depend on the lab’s reference interval and testing method. Most laboratories consider a low-teens result normal when potassium is excluded, but you should always compare the number to the reported reference interval on that specific test result.
Why is potassium often left out of the anion gap calculation?
Potassium is usually excluded because it contributes minimally to the overall result. Leaving it out creates a streamlined formula that fits common clinical practice and laboratory reporting standards without meaningfully changing everyday result interpretation.
What does a high anion gap mean clinically?
A high result suggests more unmeasured acid buildup and is often associated with metabolic acidosis, especially high anion gap metabolic acidosis. Common causes include elevated lactate states, ketosis-related acidosis, renal failure, and toxin exposure. The value helps guide evaluation, but the cause requires further workup.