What exactly is the anion gap and why does it matter in ICU?
The anion gap is a useful way to evaluate acid-base balance using a common electrolyte panel. It compares the major measured cations and anions, mainly sodium, chloride, and bicarbonate, to estimate the amount of unmeasured anions in serum. In the ICU, this matters because a rising or falling anion gap can be an early clue to a serious metabolic derangement before the patient’s condition becomes obvious clinically.
For critically ill patients, the anion gap is not just a number. It is a signal that helps shape the diagnostic approach to metabolic acidosis and other acid-base disorders. It can point toward high anion gap metabolic acidosis, identify hidden acid loads, and reveal a compensatory response that is not yet complete. Because ICU patients often have overlapping problems such as shock, kidney injury, infection, and fluid shifts, the anion gap is best interpreted in clinical context, not in isolation.
Changes in chloride and bicarbonate can also reflect a chloride shift or iatrogenic fluid effects. For example, hyperchloremia may lower the anion gap, while hypochloremia may make the gap appear elevated relative to the patient’s actual acid burden. That is why the anion gap is a starting point for interpretation, not the final answer.
How can you calculate the anion gap?
The traditional calculation uses the measured serum concentrations of sodium, chloride, and bicarbonate:
Anion gap = sodium − (chloride + bicarbonate)
A lot of clinicians use an anion gap calculator to save time and avoid arithmetic errors, especially when managing multiple patients or reviewing serial labs during fast shifts in condition. The calculator is useful, but it only works well if the input values are accurate and the result is interpreted alongside the rest of the data.
Lab methods and reference intervals can vary a bit between institutions, so the numeric result should always be compared with the local reference range. Some clinicians add potassium to the calculation as well, but the sodium-based version is most commonly used in ICU practice. The important concept is that the gap reflects the relationship between measured electrolytes and the presence of additional acid anions such as lactate, ketones, or toxic metabolites.
Because the result is derived from the basic chemistry panel, it can be repeated easily over time. That is why it is helpful for following trends, assessing response to therapy, and watching for evolving acid-base disorder patterns. Within the ICU, trending labs often matters more than a single number.
What’s a normal anion gap in critically unwell patients?
A “normal” anion gap depends on the laboratory method, the institution, and the patient’s albumin status. The local reference range may vary from what clinicians learned from training, so the printed lab interval should guide interpretation. In general, an anion gap within the reference range suggests that the major unmeasured acids are not markedly increased, but that does not fully exclude clinically important acidosis.
Albumin has a major effect because it is a negatively charged protein and a key contributor to the expected gap. In critical illness, low serum albumin is often seen, and the measured anion gap may therefore appear deceptively low. For that reason, the albumin-corrected anion gap is often more informative than the uncorrected value.
When the albumin level is reduced, a “normal” gap may actually represent a concealed increase relative to the patient’s baseline. This matters because clinicians may otherwise miss a meaningful acid burden. The result should be viewed as part of the full acid-base balance assessment, including pH, bicarbonate, respiratory compensation, and the overall clinical picture.
What leads to an elevated anion gap in intensive care?
An elevated gap usually suggests additional unmeasured anions from biologic or mineral acids. In the ICU, usual causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each has a different pathophysiology, but all widen the gap by introducing acid anions that are not directly measured on the standard chemistry panel.
Lactic acidosis is one of the most common causes in unstable patients. It may result from shock, sepsis, hypoperfusion, hypoxemia, seizures, beta-agonist exposure, or impaired lactate clearance. Because lactate can rise quickly, it is often a key target in the early diagnostic approach. A rising gap with lactate elevation strongly suggests tissue hypoperfusion or another major metabolic stressor.
Ketoacidosis may occur in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. Here, ketone bodies are the unmeasured anions driving the gap. Checking ketones how to interpret delta ratio is essential if the clinical picture includes hyperglycemia, poor intake, vomiting, or altered mental status.
Renal failure can also produce a high gap because the kidneys cannot excrete acid effectively. Retained sulfate, phosphate, urate, and other organic acids accumulate, creating a pattern of high anion gap metabolic acidosis. In advanced kidney injury, the acid burden may be substantial even before creatinine peaks, so the anion gap can serve as an earlier clue.
Toxic alcohols such as methanol, ethylene glycol, and related substances can produce severe metabolic acidosis with an elevated gap. This diagnosis is time-sensitive. The gap may be an early trigger to broaden the differential and evaluate osmolar status, neurologic findings, and exposure history.
In all of these situations, the size of the gap does not tell the whole story. Severe illness can coexist with a modest gap, and a very high gap can develop rapidly. Trend the result and compare it with the patient’s symptoms, hemodynamics, and other laboratory data.
What leads to a normal anion gap metabolic acidosis?
A normal anion gap metabolic acidosis is also called hyperchloremic acidosis because the drop in bicarbonate is often countered by a rise in chloride, keeping the gap. Typical causes include diarrhea, renal tubular acidosis, and large-volume chloride-rich fluid infusion. In these cases, the problem is not a buildup of unmeasured acids but rather a depletion of bicarbonate or a failure to recover or produce it effectively.
Diarrhea can cause significant gastrointestinal bicarbonate loss, especially when severe or extended. The body adjusts with a slight increase in chloride, leading to hyperchloremic acidosis. This pattern may be seen in septic patients, after surgery patients, and those with enteral losses.
Renal tubular acidosis includes syndromes where the kidneys cannot acidify urine or reabsorb bicarbonate properly. The result is metabolic acidosis with a normal gap, and the diagnosis often requires urine studies and careful review of the overall presentation.
Hyperchloremia from IV fluid therapy can also be a factor. Because chloride rises as bicarbonate falls, the gap stays “normal” even while the patient remains acidemic. This is one reason the ICU team should not stop at the anion gap alone when evaluating acid-base disorders.
How exactly does hypoalbuminemia affect the assessment?
Hypoalbuminemia is a major reason the calculated anion gap can confuse clinicians in the ICU. Since albumin is a primary unmeasured anion, lower levels decrease the expected gap. As a result, a patient with significant metabolic acidosis may still show a normal or only mildly elevated measured value.
The usual correction formula adjusts the gap upward when albumin is low. Different formulas exist, but the concept is the same: lower albumin means the “baseline” gap should be assumed to be lower, so the observed value must be corrected to avoid missing the acid burden. The albumin-corrected anion gap is especially useful in critical illness, where inflammation, capillary leak, malnutrition, liver dysfunction, and dilution can all decrease serum albumin.
Using the corrected value increases detection of hidden high anion gap metabolic acidosis. It can also prevent false reassurance when the uncorrected number looks acceptable. In practice, if albumin is clearly low, the corrected gap should be assessed alongside the blood gas, lactate, and the rest of the clinical picture.
In ICU interpretation, a normal measured gap with low albumin may not be truly normal.
How should you interpret the anion gap in mixed acid-base disorders?
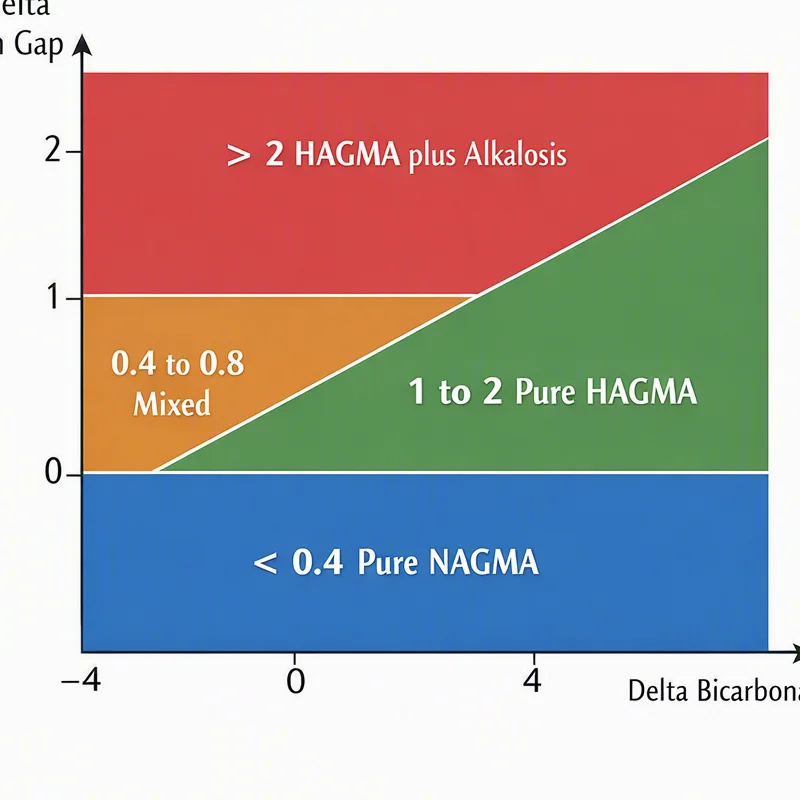
A multiple acid-base disorder is frequent in critically ill patients and can obscure important findings. A patient may have both increased anion gap acidosis and another process such as metabolic alkalosis or normal gap acidosis. The anion gap helps spot the presence of a high-gap process, but the bicarbonate and pH pattern reveal whether something else is also occurring.
The delta gap and delta-delta ratio are important tools for this evaluation. The delta gap compares the rise in anion gap above normal to the fall in bicarbonate. The delta-delta ratio helps clarify whether the change in bicarbonate is proportionate to the change in gap. If the ratio is abnormal, a second acid-base process may be present.
For example, a patient with lactic acidosis may also have vomiting-related metabolic alkalosis, or a patient with chronic kidney disease may have simultaneous respiratory compensation and hyperchloremia. Mixed disorders are common in critical illness because patients often have multiple drivers of acid-base disturbance at once.
The practical point is that a single elevated anion gap should not finish the analysis. Review the blood gas, bicarbonate, chloride, albumin, and clinical course together. The goal is not only to name the disorder but to understand what is driving the patient’s current physiology.
What are the most common ICU missteps when using an anion gap calculator?
A frequent pitfall is laboratory artifact. Contamination of the blood sample, sample handling problems, or assay interference can alter sodium, chloride, or bicarbonate values and produce a misleading gap. If the result does not fit the clinical picture, repeat testing and assess whether the specimen may have been compromised.
Another pitfall is ignoring hyperalbuminemia or assuming albumin is always low in ICU patients. Even though hypoalbuminemia is more common, unusually high albumin can increase the measured gap. This is less frequent but still relevant when there is dehydration or hemoconcentration.
Unmeasured cations can also affect interpretation. Lithium, marked hypermagnesemia, and severe hypercalcemia may decrease the gap by balancing unmeasured anions. In other words, the anion gap is affected by more than just acid production. It represents a balance of charges, so the presence of unusual cations can skew the expected result.
Other common pitfalls include overreliance on a single value, failure to account for albumin, and ignoring the effect of IV fluids on chloride. An anion gap calculator is helpful, but it should never replace bedside reasoning. The best interpretation comes from pairing the number with the patient’s hemodynamics, medications, renal function, and serial labs.
What should you do after identifying an abnormal anion gap?
When an abnormal gap is detected, the next step is to identify the likely cause and assess severity. Start with the basics: check lactate, ketones, and a blood gas. These studies help separate lactic acidosis, ketoacidosis, and other major drivers of metabolic acidosis.
Then apply clinical correlation. Ask whether the patient has shock, sepsis, renal dysfunction, toxic ingestion risk, poor intake, diarrhea, or medication exposures. Review the medication list, urine output, hemodynamics, and recent interventions such as fluid resuscitation or diuretic use.
Use the trend over time to evaluate response. Repeated labs can reveal whether the gap is widening, improving, or staying stable. That trend is often more useful than the initial measurement anion gap in chronic kidney disease because it reflects the patient’s changing physiology and the effect of treatment.
If the gap is high, address the underlying problem while supporting the diagnosis. If the gap is normal but acidosis persists, think about normal anion gap causes such as diarrhea, renal tubular acidosis, or hyperchloremic states. If the gap is unexpectedly low, review albumin and think about unmeasured cations or artifact.
In ICU care, the anion gap is a guiding tool, not a final diagnosis. It helps focus the differential, guide further testing, and sequence treatment, but it always needs to be considered alongside the broader clinical picture.
Frequently asked questions about anion gap interpretation
How does an anion gap calculator help in ICU interpretation?
An anion gap calculator accelerates the initial calculation from sodium, chloride, and bicarbonate and minimizes arithmetic errors during busy ICU workflows. It is most helpful as a baseline for interpretation, especially when you are reviewing an acid-base disorder in real time. The calculator does not substitute for clinical judgment, albumin adjustment, or follow-up testing.
Why is the anion gap lower in hypoalbuminemia?
Hypoalbuminemia decreases the gap because albumin is a major unmeasured anion. When serum albumin drops, fewer negative charges are present in the blood, so the measured anion gap falls even if an acid load is present. That is why the albumin-corrected anion gap is often favored in critically ill patients.
What is the difference between high and normal anion gap metabolic acidosis?
High anion gap metabolic acidosis suggests accumulation of unmeasured acids such as lactate, ketones, or toxins. Normal anion gap metabolic acidosis usually reflects bicarbonate loss or chloride gain, such as with diarrhea or renal tubular acidosis, and is often associated with hyperchloremia. The distinction matters because it clarifies the diagnostic approach and suggests different causes.
When do you calculate an albumin-corrected anion gap?
You should calculate an albumin-corrected anion gap whenever albumin is decreased or expected to be low, which is often seen in critical illness. It is particularly helpful when the reported gap seems normal but the patient appears to have an acid-base disturbance or another concerning acid-base disorder. Correction helps reveal hidden high-gap states.
Can a normal anion gap still occur with serious metabolic acidosis?
Yes. A patient can have serious metabolic acidosis with a normal anion gap, particularly in diarrhea, renal tubular acidosis, or chloride-rich fluid states. A normal gap does not rule out clinically important acid-base disease, so the full evaluation should include pH, bicarbonate, chloride, albumin, lactate, ketones, and the overall ICU context.