What This Measurement Shows
The anion gap value is a practical way to read serum electrolytes and determine whether the body’s acid-base balance may be disturbed. It is not a straight measurement of a single substance. Instead, it is a derived value that helps identify hidden ions in the blood when reviewing a standard electrolyte panel.
Clinically, the anion gap is commonly used to assess acidosis. This is a metabolic issue in which too much acid builds up or too much bicarbonate is lost. Because the calculation uses routine blood test results, it acts as a valuable diagnostic tool in laboratory interpretation and clinical evaluation.
An Anion Gap Calculator helps users calculate anion gap quickly and consistently, especially when they want anion gap with units explicitly shown. That matters because the value is only meaningful when the reference ranges and context are understood accurately.
In basic terms, the anion gap reflects the relationship between positively charged and negatively charged particles in blood. The main electrolytes involved are sodium, chloride, and bicarbonate. When the balance shifts, the result can point toward an electrolyte imbalance, an acid-base disorder, or a more specific condition such as high anion gap metabolic acidosis.
Formula for Anion Gap & Computation
The usual anion gap equation uses three typical serum measurements: sodium, chloride, and bicarbonate. The basic formula is:
Anion gap = sodium − (chloride + bicarbonate)
Certain labs may use a slightly different version that includes potassium, but the most common clinical formula uses serum sodium, serum chloride, and serum bicarbonate. This is the formula many people expect from an Anion Gap Calculator.
To calculate anion gap step-by-step:
- Take the serum sodium value. Add the serum chloride and serum bicarbonate values together. Deduct that total from sodium.
As an example: if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This is the main formula, but interpretation depends on the units, the reference range, and whether albumin correction is needed.
Since anion gap is a computed number rather than a directly measured electrolyte, it should always be interpreted alongside the blood chemistry pattern. A within-range number does not always rule out disease, and an unexpected result does not always mean a serious disorder without additional context.
Units Commonly Used in Anion Gap Calculation
Anion gap is often reported in mEq/L or mmol/L. In clinical use, these values are typically anion gap in chronic kidney disease numerically equivalent for the electrolytes used in the formula, which is why many clinicians and lab reports treat them similarly. That said, users should always check the laboratory units shown on the report before making assumptions.
The calculation is based on serum chemistry, so the unit formatting follows how the laboratory measures the electrolytes. Sodium, chloride, and bicarbonate are often listed as either mEq/L or mmol/L, depending on the analyzer and reporting system.
For most routine interpretation, anion gap with units does not require conversion if all components come from the same lab report. Consistency is the key point. A calculator should use values from the same electrolyte panel and preserve the same units in the final answer.
Here are the practical takeaways:
- mEq/L is common in clinical chemistry reporting. mmol/L is also widely used and often matches the numeric result. Mixed units can lead to misinterpretation, especially if a value is copied incorrectly.
When using an Anion Gap Calculator, always confirm the units before reviewing the interpretation. Even though the formula is simple, the reliability of the result depends on accurate blood chemistry data and correct laboratory units.
Standard Anion Gap Range and Lab Values
The typical range for anion gap differs by laboratory because various analyzers and reference methods may give slightly different results. That is why you should rely on the lab’s reference range rather than a single universal number.
In many settings, the anion gap is regarded normal when it stays within a modest range centered around the low teens, but the exact reference values vary. Some reports also adjust interpretation based on whether potassium is included in the formula. Because of these differences, the numeric result should always be compared with the local lab’s published values.
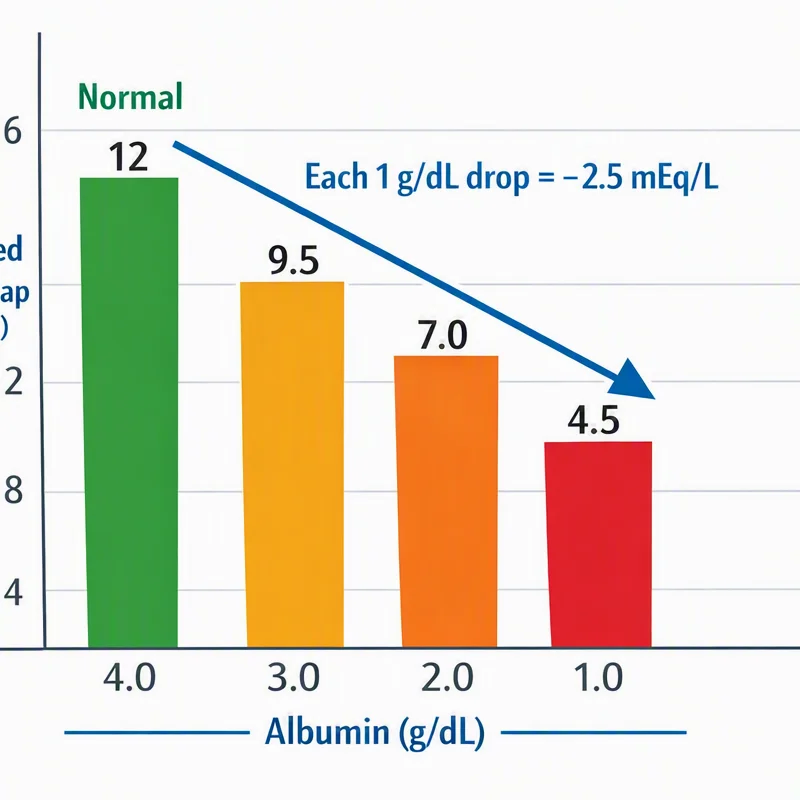
Albumin plays an key role in the normal range. Since albumin is a major unmeasured anion, a low albumin level can make the anion gap appear decreased than expected. This is why albumin correction may be required when interpreting blood test results in patients with low albumin.
The corrected anion gap is often more helpful than the raw number when albumin is reduced. This adjustment helps avoid missed recognition of an underlying acid-base disorder. If albumin is low, a apparently normal anion gap can conceal a real abnormality.
Reference values should always be interpreted in context:
- Apply the lab-specific normal range. Check whether the result is uncorrected or corrected. Consider albumin level before drawing conclusions.
High Anion Gap vs Normal Anion Gap Metabolic Acidosis
One of the key uses of the anion gap is differentiating high anion gap metabolic acidosis from normal anion gap metabolic acidosis. Both are varieties of metabolic acidosis, but they arise from distinct mechanisms and therefore point to various causes.
In high anion gap metabolic acidosis, additional acids gather in the body. These acids are not directly measured in the routine electrolyte panel, so the anion gap rises. Common examples include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
In normal anion gap metabolic acidosis, bicarbonate is lost and replaced by chloride, so the gap remains within the expected range. This is sometimes called hyperchloremic metabolic acidosis. The acid-base balance is still abnormal, but the pattern is not the same as from high-gap states.
Lactic acidosis is a major cause of high anion gap metabolic acidosis. It can occur when tissues are not receiving enough oxygen or when metabolism is significantly stressed. Ketoacidosis is another classic cause, especially when the body produces excess ketones. Renal failure can also cause retention of acids because the kidneys cannot remove them efficiently.
By contrast, normal anion gap metabolic acidosis is often associated with bicarbonate loss from the gastrointestinal tract or kidneys. The chloride shift helps preserve electrical neutrality, so the gap may seem normal even though the patient has a substantial acid-base disorder.
Frequent Causes of an Abnormal Anion Gap
An altered anion gap can indicate several relevant clinical issues, but the significance depends on whether the result is increased or reduced. For practical use, the most clinically significant abnormality is a raised result.
Ketone-related acidosis is a frequent cause of high anion gap. This may occur in diabetes, starvation, or other metabolic states where ketone production goes up. These acids raise the gap because they add unmeasured anions to the bloodstream.
Impaired kidney function can also raise the anion gap by impairing acid excretion. As kidney function deteriorates, acids accumulate, and the calculated gap increases.
Toxin ingestion is another key cause. Certain toxic substances generate unmeasured acids or interfere with metabolism, leading to increased anion gap metabolic acidosis. In clinical evaluation, this possibility should be interpret high anion gap considered when the blood chemistry pattern is atypical or severe.
Elevated lactate acidosis is often seen in sudden illness, poor tissue perfusion, or systemic stress. It is one of the major causes to detect quickly because it may reflect a severe underlying problem.
Loss of bicarbonate is more often seen in normal anion gap metabolic acidosis. While the gap may not be elevated, the bicarbonate level is decreased, and the clinical impact can still be significant.
Other possible contributors can include mixed acid-base disorders, medication effects, and changes in serum electrolytes. This is why an increased or decreased anion gap should never be interpreted in separation.
How to Understand Results Properly
Correct interpretation requires more than comparing a number with the reference range. A thoughtful clinical interpretation should consider albumin, electrolyte findings, and the possible acid-base disorder.
First, review albumin correction if the patient has low albumin. Because albumin contributes to the anion gap, reduced levels can hide a clinically relevant elevation. The corrected anion gap offers a better estimate of the true acid-base status in many cases.
Then, look for a chloride shift. If bicarbonate is low and chloride is high, the pattern may indicate normal anion gap metabolic acidosis. This does not exclude disease; it simply suggests a different mechanism than high-gap states.
Also, connect the result with the broader acid-base disorder. The anion gap is one part of the story. It should be interpreted with pH, bicarbonate, clinical symptoms, and other relevant laboratory findings when available.
A useful approach is to think in layers:
- Is the anion gap high, normal, or low? Do sodium, chloride, and bicarbonate fit together logically? Does albumin need correction because it is low? Does the full pattern align with the patient’s presentation?
This approach helps prevent common interpretation mistakes. A result should support the diagnosis, not replace clinical judgment.
When to Use an Anion Gap Calculator
This Anion Gap Calculator can be most useful when you have test values from an electrolyte panel and want a fast, dependable way to calculate the anion gap. It is especially helpful during a medical assessment if rapid blood chemistry review is needed.
Use a calculator when reviewing lab values that include sodium, chloride, and bicarbonate. These values are usually available in a standard electrolyte panel and can be entered directly without manual arithmetic errors.
A calculator is also useful when comparing multiple sets of blood test results over time. Trend analysis can reveal whether the gap is increasing, decreasing, or remaining stable. That can be useful in monitoring treatment response or identifying a worsening metabolic disturbance.
In clinical workflows, the calculator serves as a practical support tool for laboratory interpretation. It can help clinicians, students, and patients understand the relationship between serum electrolytes and acid-base balance. It is not a substitute for professional diagnosis, but it can improve clarity when reviewing blood chemistry results.
It is especially helpful when:
- Assessing possible metabolic acidosis Checking for high anion gap metabolic acidosis Evaluating low albumin and considering albumin correction Reviewing an unexplained electrolyte imbalance
Frequently Asked Questions
What is the formula for calculating anion gap?
The standard formula is sodium minus the sum of chloride and bicarbonate. In equation form, it is anion gap = sodium − (chloride + bicarbonate). This is the most common formula used by an Anion Gap Calculator.
What units are used for anion gap?
Anion gap is commonly reported in mEq/L or mmol/L. In many cases, the numeric result is the same in both formats, but you should always follow the laboratory units shown on the report.
What is a normal anion gap range?
The normal range depends on the laboratory reference range and the testing method used. Always compare the result with the local reference values rather than assuming one universal normal range.
How does low albumin affect the anion gap?
Reduced albumin can reduce the observed anion gap because albumin is a key unmeasured anion. This is why albumin correction is important; the corrected anion gap may uncover an abnormality that the uncorrected value hides.
What does a high anion gap indicate?
A high anion gap often suggests high anion gap metabolic acidosis. Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion. The result should always be read with the full clinical picture and other blood test results.