What Is Delta Gap?
The delta gap measure is a practical way to evaluate whether an acid-base condition is restricted to one process or contains more than one pattern at the same time. It is typically used when a patient has metabolic acid buildup and the anion gap is elevated. In that setting, the delta gap helps estimate whether the drop in bicarbonate matches the rise in the anion gap.
That comparison matters because a isolated episode of metabolic acidosis does not always account for the full medical importance of the lab results. If the anion gap rises more than expected, or if bicarbonate falls more than expected, the result may suggest a mixed acid-base disorder. In other words, delta gap is a simple check for hidden complexity in acid-base balance.
The concept is closely related to the anion gap delta and the delta comparison ratio. These measurements compare the change in the anion gap to the change in bicarbonate. They are not used to substitute for the rest of the evaluation, but they add a useful layer of comparison when interpreting lab electrolytes.
In basic terms:
- The anion gap shows whether unmeasured acids may be present. The delta gap shows whether the bicarbonate change fits that rise. The result helps identify a possible hidden second disorder.
How an Anion Gap Calculator Works
An anion gap calculator is a utility that uses basic electrolyte measurements to calculate the anion gap efficiently. The calculation depends on the values for serum sodium, serum chloride, and serum bicarbonate. Most calculators use the standard formula:
Anion gap = Serum sodium - (Serum chloride + Serum bicarbonate)
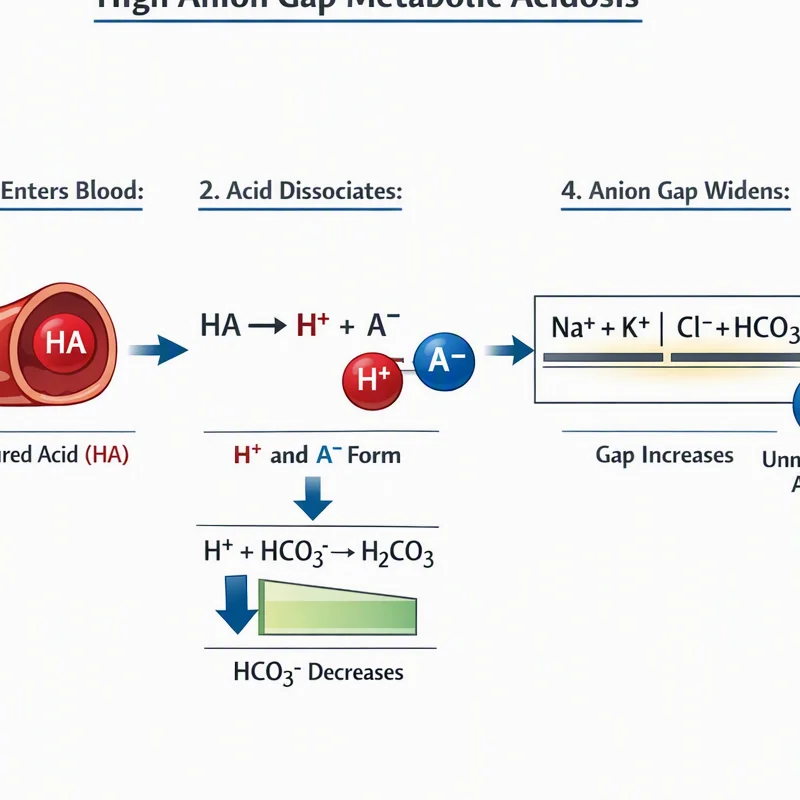
This measurement helps determine whether there is an elevated level of unmeasured anions in the blood. When the result is above the expected reference range, it may suggest the presence of metabolic acidosis, especially high anion gap metabolic acidosis.
Here is how each value matters:
- Serum sodium contributes the main positive charge in the calculation. Serum chloride accounts for one major negative charge that shifts in response to acid-base shifts. Serum bicarbonate indicates buffering capacity and often falls in metabolic acidosis.
A calculator can give a rapid result, but the clinical value comes from interpretation. The same anion gap number can have varied implications depending on the patient’s electrolytes, symptoms, and arterial blood gas findings.
For example, if serum bicarbonate is low and chloride is high, the pattern may suggest normal anion gap metabolic acidosis. If bicarbonate is low and the anion gap is elevated, the evaluation turns toward high-gap causes and possible mixed patterns.
Delta Gap Formula and Sequential Computing
The delta gap formula contrasts the observed rise in the anion gap with the anticipated fall in bicarbonate. The aim is to determine whether the change is consistent or whether something else is affecting the result.
The delta gap = Elevation in anion gap - Drop in bicarbonate
A different way to state the process is through the ratio calculation:
Ratio = (Recorded anion gap - reference anion gap) ÷ (expected bicarbonate - Measured bicarbonate)
Before you calculate, you need a reference range for the “normal” values applied in the comparison. A number of clinicians use a normal anion gap of about 12 mEq/L and a normal bicarbonate of about 24 mEq/L, but local lab ranges may differ. For that reason the reference range should always be checked against the actual laboratory report.
Step by step:
Obtain the measured anion gap from the anion gap calculator. Remove the normal anion gap to get the anion gap difference. Determine the bicarbonate deficit by subtracting the measured bicarbonate from the normal bicarbonate. Evaluate the two values using the delta gap formula or delta ratio.Worked example:
Imagine a patient has:
- Serum sodium: 140 Serum chloride: 100 Serum bicarbonate: 14
First, calculate the anion gap:
140 - (100 + 14) = 26
If the normal anion gap is 12, then the delta anion gap is:
26 - 12 = 14
If the normal bicarbonate is 24, then the bicarbonate deficit is:
24 - 14 = 10
The delta ratio is then:
14 ÷ 10 = 1.4
A result around this range often suggests a common high anion gap pattern, but the full diagnosis still depends on the patient’s overall picture. The value becomes more useful when compared with the expected pattern for the suspected cause.
How to Read Delta Gap Results
Delta gap analysis is most useful after confirming high anion gap metabolic acidosis. The result helps identify whether the acid-base disorder is isolated or whether a second process is present.
General interpretation uses the idea that the increase in anion gap should roughly match the decrease in bicarbonate. If the match is inconsistent, the result may indicate an additional disorder.
Common interpretation patterns:
- Normal or near-normal delta ratio: often in line with uncomplicated high anion gap metabolic acidosis. Low delta ratio: may suggest an added normal anion gap metabolic acidosis, because bicarbonate is falling to a greater extent than the gap is rising. High delta ratio: may suggest a concurrent metabolic alkalosis or chronic compensation, because the bicarbonate is not as low as expected for the size of the gap.
This is where mixed acid-base disorder detection becomes especially important. A single lab result can hide two different processes moving in opposite directions. The delta approach helps expose that pattern.
For example, a patient with elevated anion gap and severe diarrhea could have both high-gap acidosis and normal-gap acidosis. Another patient with vomiting and ketoacidosis could have high-gap acidosis plus metabolic alkalosis. In both cases, the delta result offers a clue that the acid-base disorder is not uncomplicated.
Always interpret the result with the arterial blood gas, symptoms, and the rest of the chemistry panel. Delta calculations are a tool for evaluation, not a final diagnosis.
Typical Reasons of Atypical Delta Gap
An unexpected delta gap often points to a cause of high anion gap metabolic acidosis or a blend of conditions. The important step is to link the pattern with likely causes and the patient’s overall picture.
Lactic acidosis is a well-known source. In this state, lactate rises and raises the anion gap. If the bicarbonate drop is larger than anticipated, a second process may also be occurring.
Ketoacidosis is one more classic reason. This can occur with diabetic ketoacidosis, starvation, or alcohol-related states. The anion gap becomes increased as ketones rise, and the delta gap can help identify whether there is also a normal-gap acidosis or a metabolic alkalosis.
Renal failure can also lead to a high gap because the kidneys are not as able to clear acids. In advanced renal dysfunction, the pattern may be altered by changes in chloride and bicarbonate management.
Toxic ingestion is an essential consideration when the anion gap is increased. Certain toxins can cause severe metabolic acidosis with an abnormal delta result. In these situations, the delta gap should be read alongside history, exam findings, and the broader metabolic picture.
Other causes of abnormal results can include:
- Marked dehydration with electrolyte shifts Various simultaneous disorders affecting chloride and bicarbonate Adaptive patterns that change the apparent bicarbonate deficit
The practical question is not only “Is the anion gap elevated?” but also “Does the bicarbonate change match the gap change?” That assessment is where the delta gap becomes useful.
Delta Gap versus Anion Gap: How Do They Differ?
The anion gap and delta gap are related, but they answer different points. The anion gap asks whether additional anions are present in surplus. The delta gap asks whether the size of the bicarbonate change corresponds to the size of the anion gap change.
Put simply:
- The anion gap is the primary screen for an acid-base problem. The delta ratio and delta gap are next-step tools for advanced acid-base evaluation.
The delta ratio is often regarded interchangeably with delta gap in clinical discussions, although the exact formula may be shown differently. Both methods aim to compare the increase in anion gap with the decrease in bicarbonate. That comparison helps reveal whether a second disorder is present.
For acid-base evaluation, the difference matters because the anion gap alone may overlook a hidden pattern. A anion gap in chronic kidney disease normal-looking bicarbonate level can conceal a mixed disorder, and a high gap can appear with another process that shifts chloride or bicarbonate in the opposite direction.
So, the main difference is purpose:
- Anion gap: identifies an abnormal measurement pattern. Delta gap: analyzes the pattern and tests for mixed disorders.
When to Use Delta Gap in Clinical Practice
Delta gap is most useful when the clinical question is focused on metabolic acidosis and the lab values are already pointing to a high-gap process. It is not often the first calculation, but it is a valuable follow-up tool when the pattern is not obvious.
You should use delta gap when:
- The patient has abnormal electrolytes and low serum bicarbonate. The arterial blood gas shows acidemia and the chemistry panel points to metabolic acidosis. You need to assess whether there is a hidden second disorder. The patient may have metabolic alkalosis with acidosis.
In practice, this is a clinical assessment tool that works best after the initial diagnosis of metabolic acidosis is already on the table. It helps answer the question: “Is this only a high-gap process, or is something else happening too?”
Delta gap is particularly valuable when:
- There is suspected lactic acidosis or ketoacidosis. The bicarbonate level seems too low for the gap. The chloride level appears to be shifting the acid-base pattern. The patient’s symptoms do not match a simple one-disorder explanation.
Because this calculation depends on precise lab values, small measurement differences can affect the result. Always verify the serum sodium, serum chloride, and serum bicarbonate values before making a decision.
Common Questions About Delta Gap
How can you determine delta gap from an anion gap calculator result?
First, apply the anion gap calculator to find the anion gap from serum sodium, serum chloride, and serum bicarbonate. Next subtract the normal anion gap to get the delta anion gap. Afterward, subtract the measured bicarbonate from the normal bicarbonate to get the bicarbonate deficit. Compare the two values using the delta gap formula or the delta ratio. This provides a quick estimate of whether the acid-base pattern is consistent or mixed.
What does a high delta gap mean?
A high delta gap often means the rise in anion gap is larger than the fall in bicarbonate. That can suggest an additional process such as metabolic alkalosis or chronic compensation. It may also mean the expected relationship between the gap and bicarbonate is not fitting the usual pattern for metabolic acidosis. The result should be interpreted with the rest of the clinical data, not alone.
What is the difference between delta gap and delta ratio?
Both terms are used to compare the change in anion gap with the change in bicarbonate. The delta ratio is usually written as a ratio, while delta gap may refer to the same comparison in a slightly different format. In practical acid-base evaluation, both aim to detect a mixed acid-base disorder and clarify the pattern behind high anion gap metabolic acidosis.
Can a normal anion gap still have a mixed acid-base disorder?
Yes. A normal anion gap does not rule out a mixed disorder. A patient can have normal anion gap metabolic acidosis plus another condition, or one process can offset another and create a misleading result. That is why the overall acid-base HAGMA causes list balance, arterial blood gas, and electrolyte pattern all matter during evaluation.
At what point should delta gap be applied in metabolic acidosis?
Delta gap should be used after metabolic acidosis has been identified and the anion gap is elevated or potentially changing the pattern. It is especially helpful when you want to determine whether the result reflects only high anion gap metabolic acidosis or whether there is also normal anion gap metabolic acidosis or metabolic alkalosis. In short, use it when the diagnosis needs a deeper comparison of bicarbonate and the anion gap.